This Medicare Payment Systems educational tool explains how each service type payment system works.
A Prospective Payment System (PPS) refers to several payment formulas when reimbursement depends on predetermined payment regardless of the intensity of services provided. Medicare bases payment on codes using the classification system for that service (such as Diagnosis-Related Groups (DRGs) for hospital inpatient services and Ambulatory Payment Classification (APC) for hospital outpatient claims).
This tool explains the payment systems for inpatient hospitals, hospice, hospital outpatient, inpatient psychiatric facilities, inpatient rehabilitation facilities, long-term care hospitals, ambulatory surgical centers, durable medical equipment, prosthetics, orthotics, and supplies, home health, and skilled nursing facilities.
Acute Care Hospital Inpatient Prospective Payment System
What’s Changed?
- Updated the hospital market basket increase
- Updated the number of Medicare Severity Diagnosis-Related Groups (MS-DRGs)
- Updated the dates for the Medicare-Dependent Hospital (MDH) Program
- Updated information on temporary changes for low-volume hospitals
- Added the FY 2027 qualifications for a low-volume hospital to get the 0.25 payment adjustment
Substantive content changes are in dark red.
Hospitals that contract with Medicare to deliver acute inpatient hospital care agree to accept predetermined acute care hospital Inpatient Prospective Payment System (IPPS) rates as full payment.
The IPPS benefit covers Medicare patients for 90 days of care per episode of illness, with a 60-day lifetime reserve. An episode of care starts when the hospital admits the patient and ends after they’ve been out of the hospital or skilled nursing facility (SNF) for 60 consecutive days.
CMS makes updates to IPPS payment rates, including updates to base rates, wage indexes, Medicare Severity Diagnosis-Related Group (MS-DRG) definitions and weights, and the outlier fixed-loss amount. We update IPPS base rates annually based on the applicable market basket index and estimates of changes in productivity.
For FY 2027, the increase in IPPS operating payment rates is 2.3% for general acute care hospitals that successfully participate in the Hospital Inpatient Quality Reporting (IQR) Program and are meaningful electronic health record (EHR) users. This reflects a projected FY 2027 IPPS hospital market basket update of 3.2% reduced by a 0.9 percentage-point productivity adjustment.
In setting the operating rate update, Congress considers the projected increase in the hospital market basket index, which measures increases in the prices of goods and services that hospitals buy to provide patient care.
We pay acute care hospitals an IPPS payment per inpatient case or discharge.
The admitting hospital, or an entity wholly owned or operated by the admitting hospital, must bill all outpatient diagnostic services and admission-related outpatient non-diagnostic services during the 3 days before admitting the patient to the hospital on the inpatient claim. Acute care hospitals can’t separately bill Medicare Part B for these services.
Section 1886(d)(1)(B) of the Social Security Act excludes certain hospitals and hospital units from the IPPS, including:
- Cancer hospitals
- Children’s hospitals
- Extended neoplastic disease care hospitals
- Hospitals located outside the 50 states, the District of Columbia, and Puerto Rico, including hospitals in:
- American Samoa
- Guam
- Northern Mariana Islands
- U.S. Virgin Islands
- Inpatient psychiatric facility hospitals and units
- Inpatient rehabilitation facility hospitals and units
- Long-term care hospitals (LTCHs)
- Religious nonmedical health care institutions
Medicare Severity Diagnosis-Related Groups
We assign inpatient hospital discharges to MS-DRGs, which we use to reflect patients’ illness severity, service complexity, and hospital resource use. We don’t make additional payments when the present on admission (POA) indicator is N, U, or 1 for certain hospital-acquired conditions (HACs). We define an MS-DRG by a group of similar clinical conditions and services requiring similar resource use. There are 768 MS-DRGs for FY 2027.
The patient’s principal diagnosis, secondary diagnoses, procedures performed, sex, age, and discharge status determine MS-DRG assignment. We consider up to 25 diagnoses and 25 procedure codes for MS-DRG assignment. We review MS-DRG classifications annually and make adjustments to reflect changes in treatment patterns, technology, and any other factors that may change the relative use of hospital resources.
If our review shows that subsets of clinically similar cases within an MS-DRG use significantly different resources, we may propose reassigning them to different MS-DRGs with similar resource use or creating new MS-DRGs.
The 3 levels of severity in the MS-DRG system, which are based on secondary diagnosis codes, are:
- Major complication or comorbidity (MCC)—diagnosis with the highest level of severity affecting hospital resource use
- Complication or comorbidity (CC)—diagnosis with a moderate level of severity affecting hospital resource use
- Non-complication or comorbidity (non-CC)—diagnosis with the lowest level of severity, which doesn’t significantly affect illness severity and hospital resource use
Some MS-DRGs are subdivided (or split) into 2 or 3 severity levels according to these CC subgroups. MS-DRGs that aren’t subdivided into severity levels are known as base MS-DRGs.
Base Payment Amounts
We set operating and capital IPPS base rates (known as the standardized payment amounts).
Operating costs cover:
- Labor
- Supplies
Capital-related costs cover:
- Depreciation
- Interest
- Rent
- Property-related insurance and taxes
We annually adjust these payment rates for:
- The patient’s clinical condition and related treatment costs compared to average Medicare case costs (MS-DRG relative weight)
- Market conditions in the hospital’s location compared to national conditions (wage index)
Other IPPS Hospital Payment Adjustments
- Acute care hospitals’ extremely high-cost cases may qualify for outlier payments.
- We pay hospitals that train residents in approved graduate medical education (GME) programs separately for the direct cost of training residents (direct GME). We also increase these IPPS hospitals’ operating and capital payment rates so they reflect teaching hospitals’ higher indirect patient care costs relative to those of non-teaching hospitals (indirect medical education (IME)).
- We increase hospitals’ operating and capital payment rates for treating a disproportionate share of low-income patients. These hospitals also get uncompensated care payments.
- We may pay acute care hospitals to treat patients with certain newly approved, costly technologies that offer a substantial clinical improvement over existing treatments or that get certain FDA designations for breakthrough devices and antimicrobial products.
- Qualifying rural hospitals and critical access hospitals (CAHs) can get pass-through payments for certain certified registered nurse anesthetist services.
- We pay for nursing and allied health education activities on a reasonable cost basis subject to the conditions and limitations in 42 CFR 413.85(d).
- We pay reasonable and necessary costs for a hospital to get an organ as an adjustment to the hospital’s IPPS payment.
- We make an add-on payment to hospitals for the costs of administering blood clotting factors to inpatients with hemophilia.
- We make an add-on payment to hospitals participating in a National Institutes of Health-sponsored islet cell transplantation clinical trial for patients with type 1 diabetes.
- We adjust IPPS payment for the added costs of buying U.S.-made, National Institute of Occupational Safety and Health-approved surgical N95 respirators.
- We adjust IPPS payment to certain small, independent hospitals for establishing and maintaining a buffer stock of essential medicines.
- We reduce payment in some cases when a patient has a short length of stay (LOS) and transfers to another acute care hospital or, in certain circumstances, to a post-acute care setting.
- We adjust IPPS payments under the Hospital Value-Based Purchasing (VBP) Program and the Hospital Readmissions Reduction Program (HRRP).
- The HAC Reduction Program reduces overall IPPS payments for reasonably preventable HACs.
- We make an add-on payment to low-volume hospitals that meet certain mileage and discharge criteria.
How We Determine an IPPS Payment
- The hospital submits a claim to its Medicare Administrative Contractor (MAC) for each patient. Using the claim information, the MAC assigns the case to an MS-DRG.
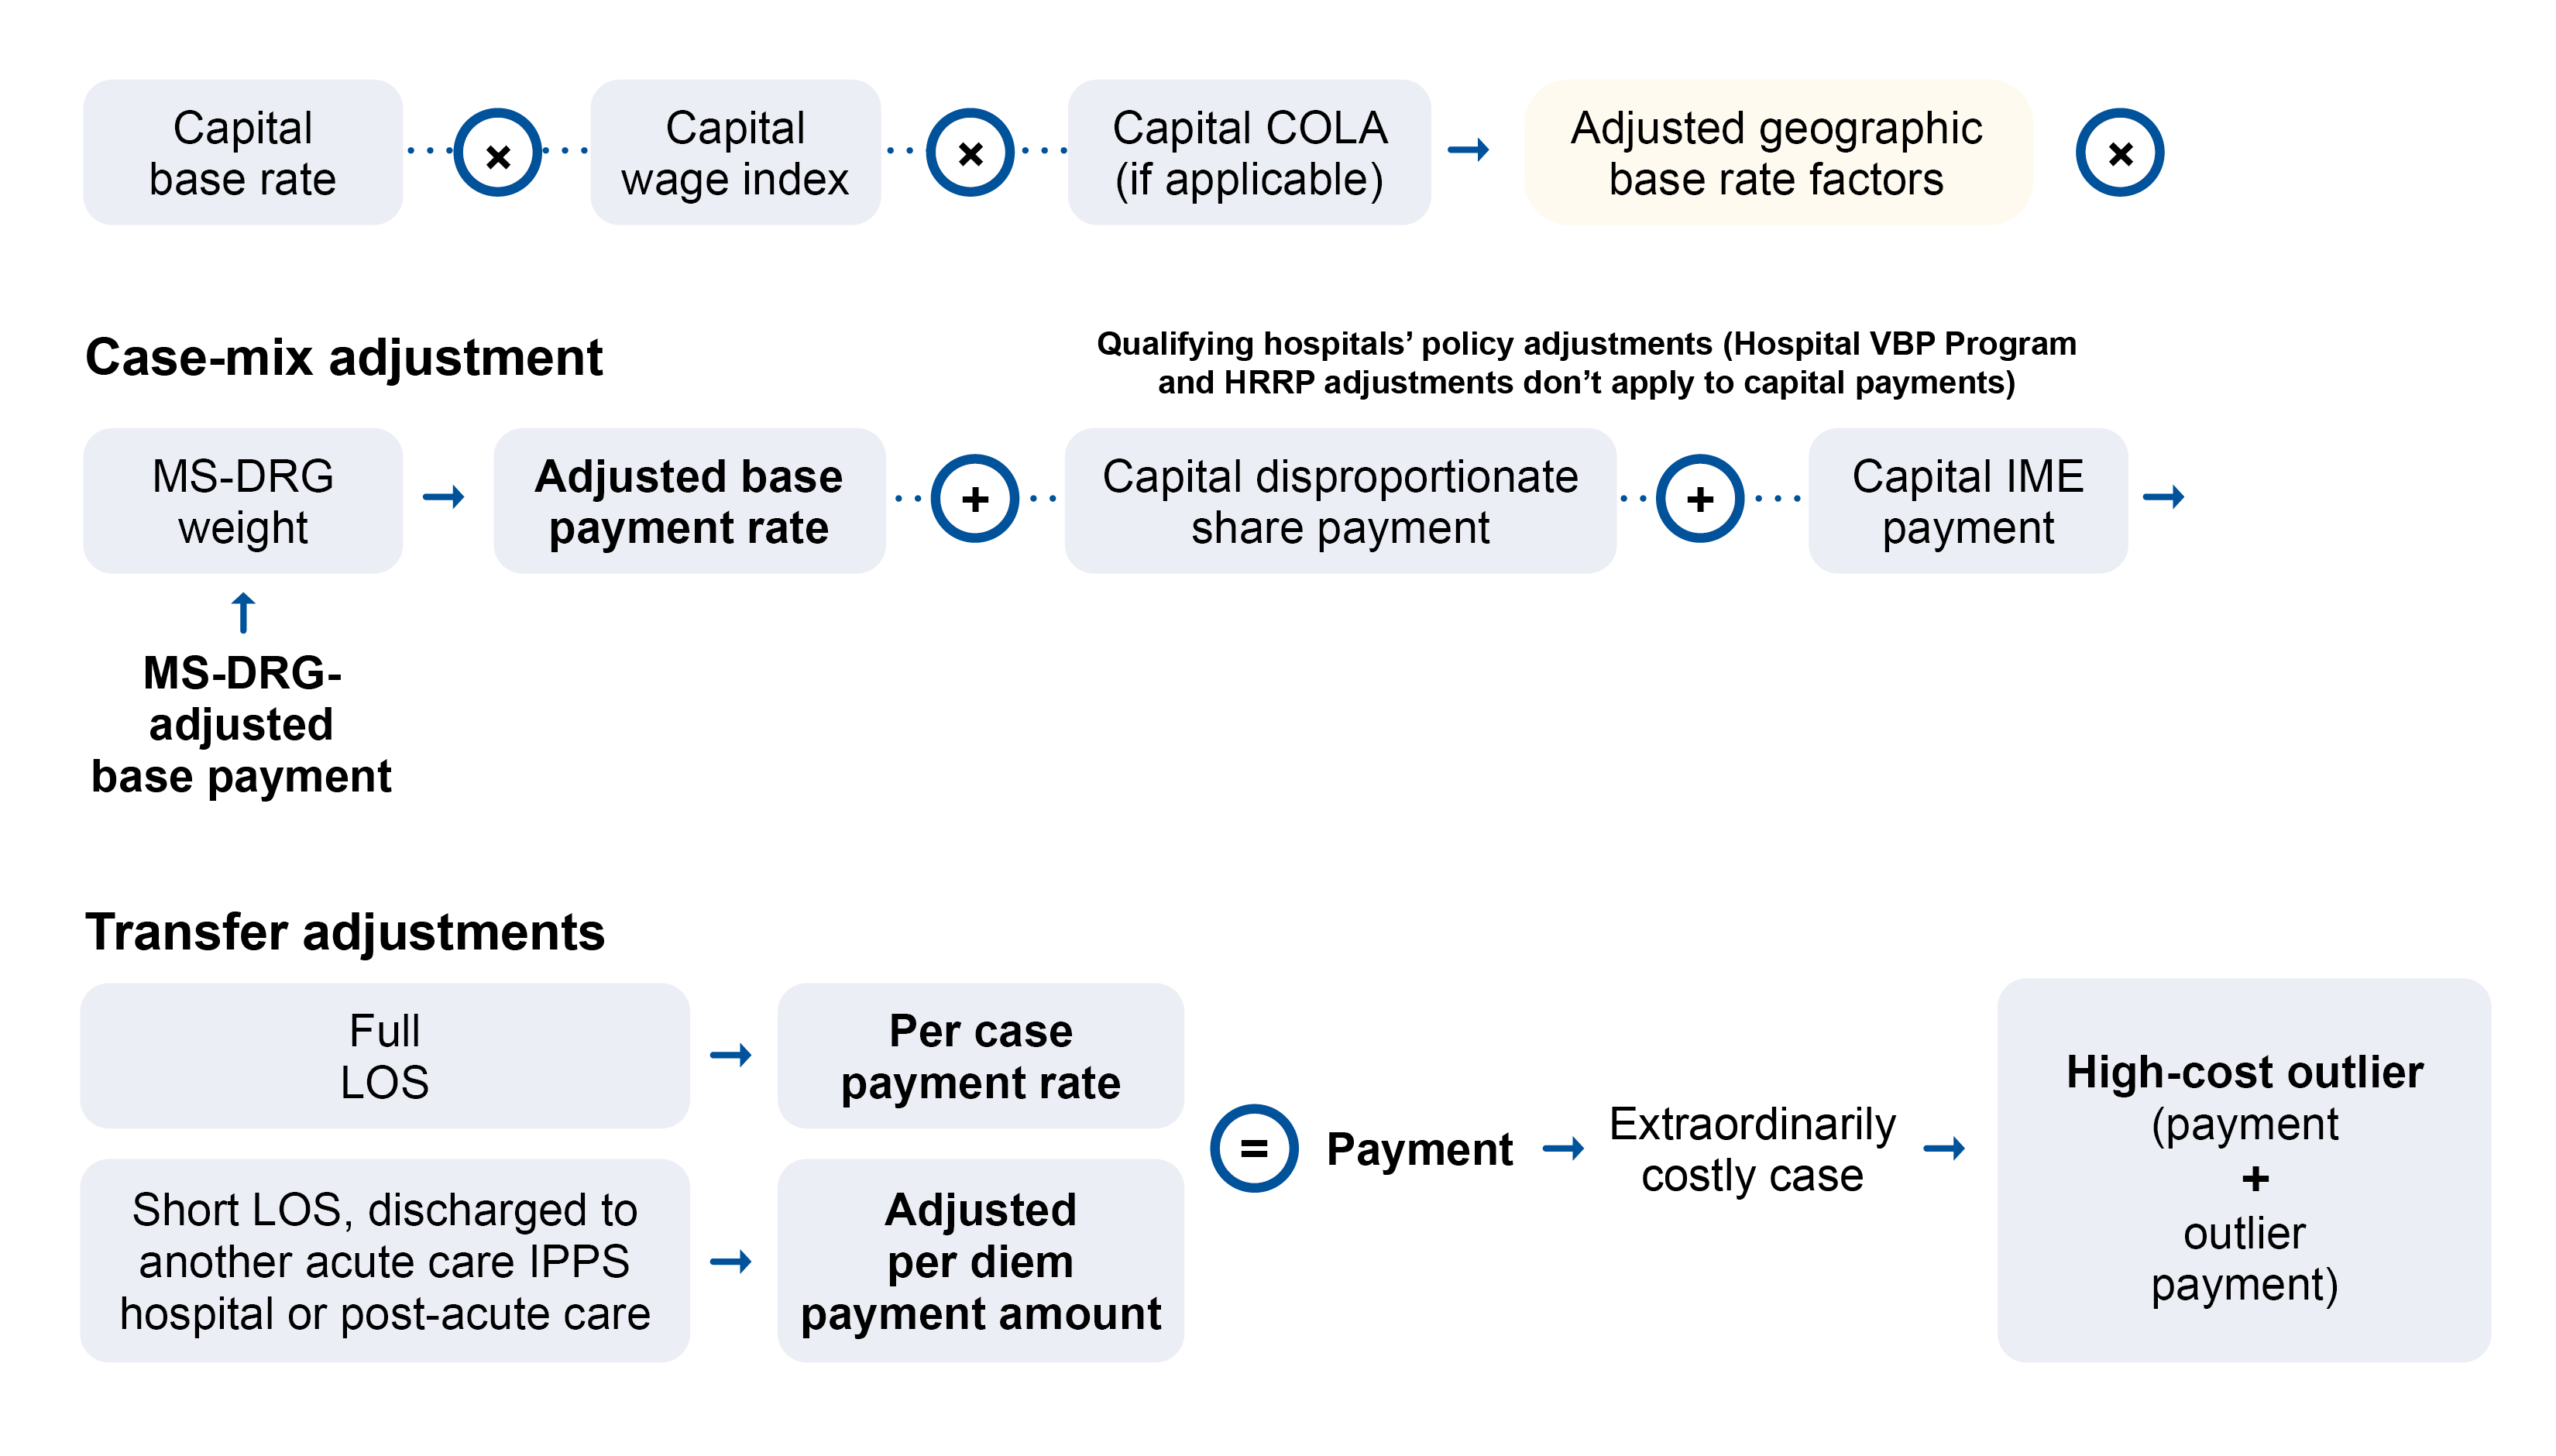
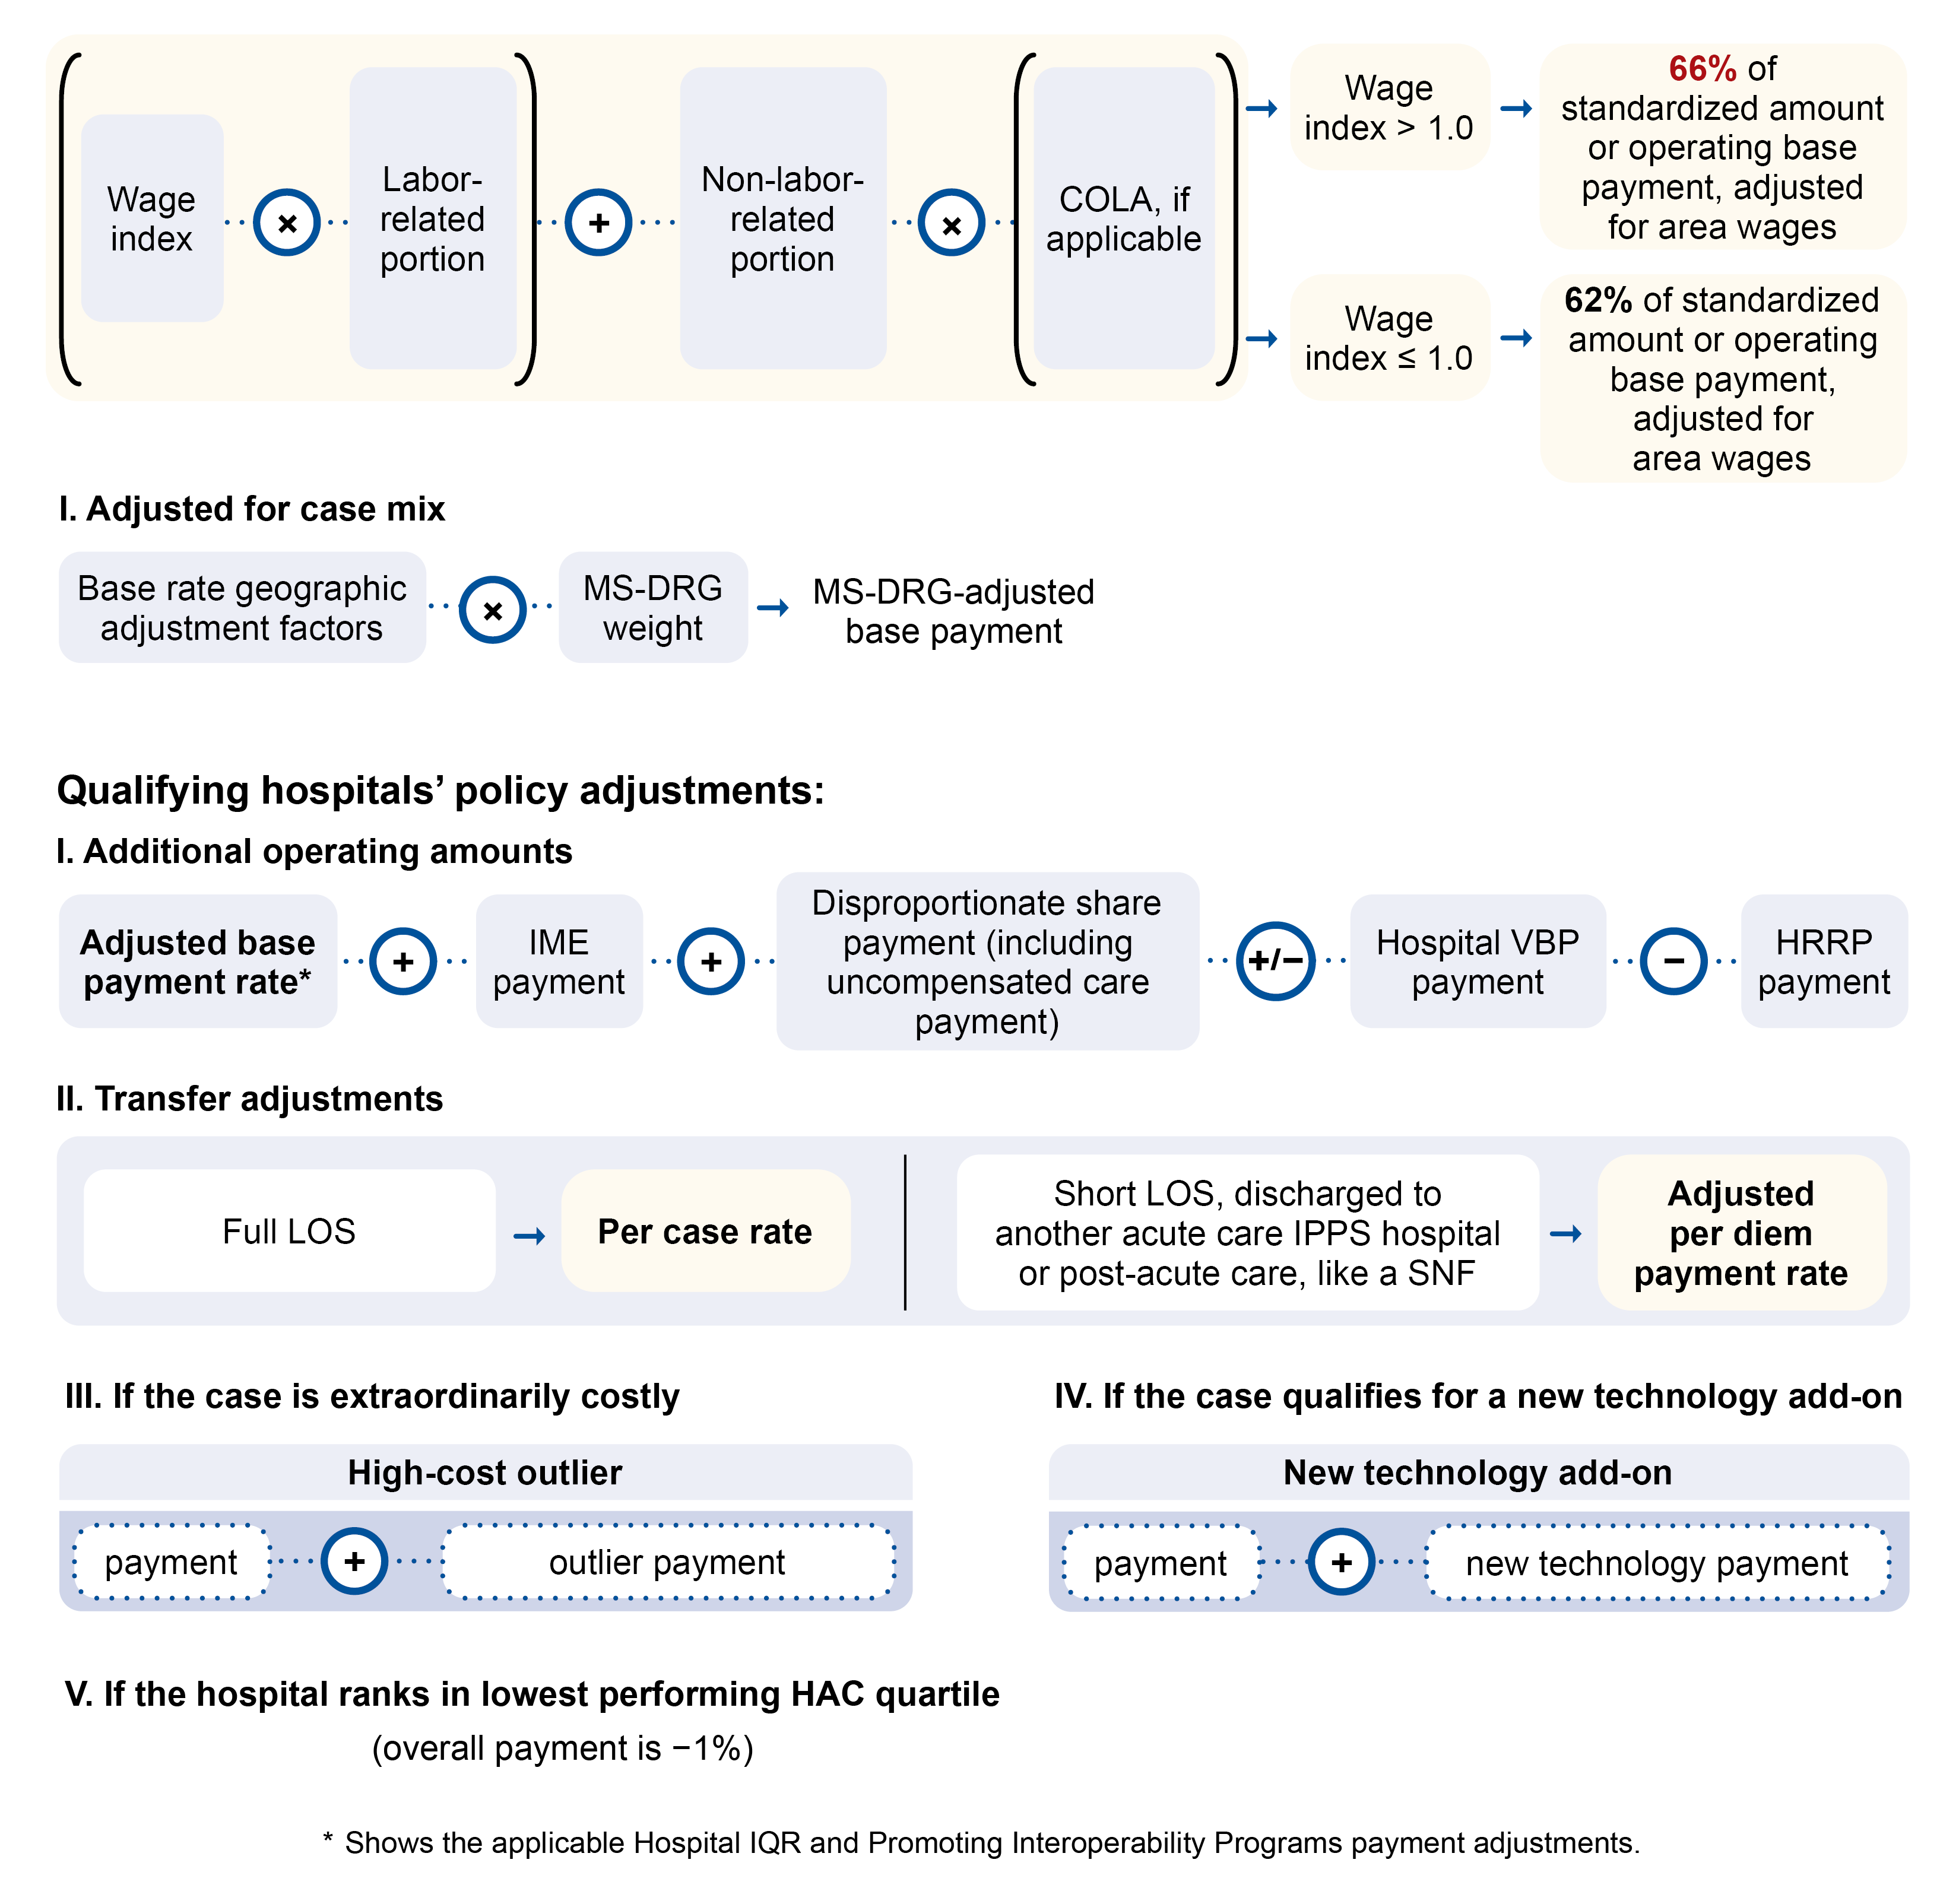
- The base payment rate, or standardized dollar amount, includes the labor-related and non-labor-related shares. We adjust the labor-related share by a wage index to reflect area labor cost differences. Starting with FY 2026 discharges, the labor-related share equals 66% if the hospital’s wage index is greater than 1.0. The law requires that the labor-related share equal 62% if the hospital’s wage index is less than or equal to 1.0. We adjust the non-labor-related share by a cost-of-living adjustment (COLA) factor for hospitals in Alaska and Hawaii to account for the higher cost of living in those states.
- We multiply the wage-adjusted standardized amount by an MS-DRG weighting factor. The weight is specific to each MS-DRG, and each MS-DRG relative weight represents the average resources used to treat cases in that MS-DRG compared to the average resources used to treat cases in all MS-DRGs.
MS-DRG Relative Weights
We assign a weight to each MS-DRG that reflects the average case cost in that group compared to the average Medicare case cost, and we use the same MS-DRG weights for operating and capital payment rates.
We annually adjust the MS-DRG weights without affecting overall IPPS payments, based on standardized charges and all IPPS case costs in each MS-DRG. This adjustment includes a 10% cap on decreases in an MS-DRG relative weight from the previous FY. We standardize hospitals’ billed charges to improve comparability by adjusting charges to remove differences in:
- Hospital wage rates across labor markets
- Size and intensity of hospitals’ resident training activities
- Number of low-income inpatients treated
Note: We reduce charges to costs using national average hospital cost-to-charge ratios for 19 different cost centers.
Market Condition Adjustments
We adjust the operating and capital rates by an area wage index to reflect differences in local labor market prices. We measure these differences by comparing the average hourly wage (AHW) for hospital workers in each urban or statewide rural area to the national average.
We use the Office of Management and Budget’s Core-Based Statistical Area delineations, with some modifications, to define each labor market area and annually revise the wage index based on IPPS hospital wage data.
If a hospital believes it competes for labor in an area different from its location, it may request geographic reclassification through the Medicare Geographic Classification Review Board (MGCRB).
These policies also apply to the wage index. Specifically, we apply:
- A permanent 5% cap on any decrease to a hospital’s wage index from its wage index in the previous year, regardless of what caused the decline.
- The wage index to the whole capital base rate and raise it to a fractional power, narrowing the geographic variation in wage index values among labor market areas.
- A COLA, reflecting higher supply and other non-labor resource costs, to the base IPPS operating and capital rates of hospitals in Hawaii and Alaska. We apply the COLA to the non-labor-related portion of the operating base rate and to the whole capital base rate.
Bad Debts
Bad debts are when a patient doesn’t pay their Medicare coinsurance and deductible. We may pay a hospital for Medicare bad debts at 65% of the allowable amount if the bad debts meet all criteria under 42 CFR 413.89.
Providers can collect unpaid patient Medicare cost-sharing amounts unless both:
- The state Medicaid agency classifies the patient as categorically or medically needy
- The provider determines the patient is indigent for bad debt purposes
Providers must submit an acceptable cost report with a detailed bad debt listing corresponding to their claimed bad debt amounts.
Direct Graduate Medical Education
We pay teaching hospitals—or hospitals that train residents in approved medical allopathic, osteopathic, dental, or podiatric residency programs—for direct GME (DGME). These payments are for the approved residency training programs’ direct operating costs.
We pay these separately from the IPPS per discharge payment and generally base DGME payments on:
- The hospital-specific costs per resident in a historical base year, updated for inflation
- The number of residents a hospital trains
- The hospital’s Medicare patient load (the proportion of Medicare inpatient days to total inpatient days)
Indirect Medical Education
Teaching hospitals—or hospitals that train residents in approved medical allopathic, osteopathic, dental, or podiatric residency programs—also get an IME adjustment, which reflects the higher indirect patient care costs of teaching hospitals relative to those of non-teaching hospitals. We calculate the IME adjustment factor using a hospital’s ratio of interns and residents to beds.
Medicare Disproportionate Share Hospitals
We also pay for inpatient operating and capital costs to hospitals that serve a disproportionate share of low-income patients.
Hospitals get 25% of the amount they previously got under the traditional Medicare disproportionate share hospital (DSH) statutory formula. The remainder—equal to 75% of what we otherwise would pay as Medicare DSH operating payments, reduced by the percentage change in uninsured individuals—goes toward an uncompensated care payment.
Each Medicare DSH gets an uncompensated care payment based on its share of uncompensated care costs compared to all Medicare DSHs. We annually update the factor estimates that determine each eligible DSH’s uncompensated care payment.
For most Medicare DSHs, we calculate uncompensated care payments from the most recent years of audited Worksheet S-10 data to determine each Medicare DSH’s share of uncompensated care payments. For FY 2024 and subsequent years, we use an average of the uncompensated care data from the 3 most recent FYs for which audited data is available.
Note: For Indian Health Service hospitals, tribal hospitals, and hospitals in Puerto Rico, we use the same multiyear average of Worksheet S-10 data to determine Factor 3 for FY 2024 and subsequent FYs. We also established a new supplemental payment for these hospitals under 42 CFR 412.106(h).
Sole Community Hospitals
A Medicare IPPS hospital is eligible for sole community hospital (SCH) classification if it’s located more than 35 miles from other like hospitals or it’s located in a rural area (as defined in 42 CFR 412.64) and meets 1 of the criteria in 42 CFR 412.92.
We don’t consider a nearby hospital to be a like hospital if its total inpatient days are less than or equal to 8% of similarly calculated total inpatient days of the hospital seeking SCH status. We base:
- An SCH’s operating payments on the higher of the federal rate payment or its hospital-specific rate payment
- An SCH’s capital payments on the capital base rate (as with all other IPPS hospitals)
SCHs may qualify for a payment adjustment if they experience a significant volume decrease.
For IPPS purposes, we treat certain hospitals formerly designated as essential access community hospitals (EACHs) as SCHs.
Medicare-Dependent Hospitals
A Medicare IPPS hospital is eligible for Medicare-dependent hospital (MDH) classification if it meets the criteria in 42 CFR 412.108.
We base MDH operating payments on the higher of the federal rate payment or the federal rate payment plus 75% of the difference between the federal rate payment and the MDH’s hospital-specific rate payment.
MDHs may qualify for a payment adjustment if they experience a significant volume decrease.
Section 6202 of the Consolidated Appropriations Act, 2026 extended the MDH Program through December 31, 2026. Starting with discharges on or after January 1, 2027, all hospitals that previously qualified for MDH status will no longer have MDH status, and claims processing and payment will be based on the federal rate.
Rural Referral Centers
The Rural Referral Center (RRC) Program supports high-volume rural hospitals. We generally classify a Medicare-participating acute care hospital as an RRC if it’s in a rural area for IPPS payment purposes and meets the criteria in 42 CFR 412.96.
Current and former RRCs get certain advantages:
- Proximity for MGCRB Reclassification: A hospital currently designated as an RRC doesn’t need to demonstrate proximity to the area into which it gets reclassified. A hospital can apply for reclassification to the closest urban or rural area.
- AHW Data Comparison for MGCRB Reclassification: We exempt hospitals currently or previously designated as RRCs from the AHW requirement that a hospital’s AHW must exceed, by a certain percentage, the AHW of the labor market area where the hospital is located. In addition, regardless of whether it’s located in an urban or rural area, a currently or previously designated RRC must only meet the rural requirement (82%) for the comparison of the hospital’s AHW with its desired reclassified area.
- Medicare DSH Cap: We exempt hospitals currently designated as RRCs from the 12% cap on Medicare operating DSH payments applicable to other rural hospitals.
Low-Volume Hospitals
Section 6201 of the Consolidated Appropriations Act, 2026 extended the temporary changes to the qualifying criteria and payment adjustment methodology for certain low-volume hospitals through FY 2026 and the portion of FY 2027 ending December 31, 2026.
For FY 2019 through the portion of FY 2027 ending December 31, 2026, we make add-on payments to a qualifying low-volume hospital more than 15 road miles from the nearest subsection (d) hospital if its most recently submitted cost report indicates it discharged fewer than 3,800 total patients during the FY. For each Medicare patient discharge:
- For qualifying low-volume hospitals with 500 or fewer total discharges, the payment adjustment is 0.25
- For qualifying low-volume hospitals with more than 500 but fewer than 3,800 total discharges, we calculate a low-volume hospital payment adjustment as 0.25 − (0.25 / 3,300) × (number of total discharges − 500) = (95 / 330) − (number of total discharges / 13,200)
Starting January 1, 2027, and for subsequent FYs, to qualify for the 0.25 payment adjustment, a hospital must have fewer than 200 total discharges and be located more than 25 road miles from the nearest IPPS hospital, consistent with 42 CFR 412.101(b)(2)(i).
Outlier Payments
We make additional payments for extremely costly outlier cases to promote seriously ill patients’ access to high-quality inpatient care. We identify these cases by comparing their estimated operating and capital costs to a fixed-loss threshold.
We annually set the fixed-loss threshold and adjust it to reflect local labor market costs.
We pay for outliers by making offsetting reductions in the operating and capital base rates (reducing the payment rates for all cases so outlier payments don’t increase or decrease estimated aggregate Medicare spending).
We set the national fixed-loss threshold at 5.1% of total FY payments. We factor projected operating outlier payment reconciliations into our outlier threshold calculation.
Transfer Policy
We reduce MS-DRG payments when the patient’s LOS is at least 1 day less than the geometric mean MS-DRG LOS and the hospital transfers the patient to 1 of these:
- Another IPPS-covered acute care hospital or, for certain MS-DRGs, a post-acute care setting
- A hospital not participating in Medicare
- A CAH
Our transfer policy applies to these post-acute care settings:
- Cancer hospitals
- Children’s hospitals
- Home health care, when the patient gets clinically related care that starts within 3 days after a hospital stay
- Hospice care
- LTCHs
- Psychiatric distinct part units located in an acute care hospital or a CAH
- Psychiatric facilities
- Rehabilitation distinct part units located in an acute care hospital or a CAH
- Rehabilitation facilities
- SNFs
New Technology Add-On Payments
We make an additional payment for new medical services and technologies that meet the criteria in 42 CFR 412.87(b).
Certain new transformative devices and antimicrobial products may qualify under an alternative inpatient new technology add-on payment pathway, discussed in 42 CFR 412.87(c) and (d).
The Medicare Electronic Application Request Information System™ (MEARIS™) allows users to submit:
- New technology add-on payment applications
- Requests for ICD-10 Procedure Coding System procedure codes
- MS-DRG classification change requests
Note: We accept MS-DRG classification change requests only if they’re submitted through MEARIS™. We no longer accept email requests.
Hospital Readmissions Reduction Program
HRRP is a Medicare VBP program that encourages hospitals to improve communication and care coordination to better engage patients and caregivers in discharge plans and, in turn, reduce avoidable readmissions. HRRP supports the national goal of improving health care for Americans by linking payment to the quality of hospital care.
We include readmission measures for specific conditions or procedures that significantly affect the lives of many Medicare patients. Under HRRP, we reduce payments to hospitals with higher-than-expected rates of readmission following treatment for select conditions and procedures, encouraging hospitals to provide high-quality care and reduce avoidable returns to the hospital.
Hospital Value-Based Purchasing Program
The Hospital VBP Program delivers upward, downward, or neutral adjustments to participating hospitals’ base operating MS-DRG payments. These adjustments are based on the hospitals’ quality measure performance. The Hospital VBP Program generally applies to all acute IPPS hospitals, with certain exceptions.
We fund value-based incentive payments by reducing hospitals’ base operating MS-DRG payment amounts by 2%. Each hospital then may earn back a value-based incentive payment that’s more than, equal to, or less than the 2% reduction, depending on their measure performance.
Hospital-Acquired Condition Reduction Program
A HAC is a condition a patient gets during hospitalization (the condition wasn’t present on admission). The HAC Reduction Program is a VBP program that links Medicare payments to health care quality in the inpatient hospital setting.
Under the HAC Reduction Program, we rank hospitals on their total of preventable conditions. We reduce overall Medicare IPPS payments by 1% for hospitals that rank in the worst-performing quartile of all hospitals on measures of HACs.
The Hospital IQR Program provides quality-of-care information so patients can make informed decisions about their health care. It also encourages hospitals and providers to improve their quality of inpatient care by making sure they’re aware of, and reporting on, best practices for their facilities.
Find current quality reporting measures on IQR Measures.
The Medicare Promoting Interoperability Program is a quality program with the goal of improving the quality, safety, and efficiency of health care by promoting the interoperability and exchange of health care data using certified electronic health record technology (CEHRT). Eligible hospitals and CAHs submit data demonstrating their meaningful use of CEHRT to CMS.
Hospitals that don’t meet reporting requirements get a 1/4 reduction to the percentage increase in the market basket index. For hospitals that aren’t meaningful EHR users and don’t get an exemption, 3/4 of the percentage increase is further reduced by 100%.
Resources
Ambulatory Surgical Center Payment System & Coverage
What’s Changed?
Note: No substantive content updates.
Ambulatory surgical centers (ASCs) provide outpatient surgical services to patients who don’t need hospitalization and typically are discharged less than 24 hours after admission. Medicare ASC patients don’t typically need active medical monitoring at midnight on the procedure day.
Medicare-certified ASCs must enter into a legal agreement with us to get paid. An ASC can be:
- Independent (not part of a service provider or other facility)
- Hospital-operated (under a hospital’s common ownership, licensure, or control) if the ASC:
- Is a separately identifiable and certified facility and is Medicare-enrolled with a supplier approval agreement distinct from the hospital’s Medicare provider agreement
- Is physically, administratively, and financially independent and distinct from other hospital operations, with its costs treated as a non-reimbursable cost center on the hospital’s cost report
- Agrees to the same assignment, coverage, and payment rules as independent ASCs
- Is surveyed and approved as complying with the ASC conditions for coverage (CfCs)
A hospital-operated ASC isn’t like a provider-based outpatient surgery hospital department.
A provider-based outpatient hospital department, including an outpatient surgery department:
- May be on or off campus
- Is an integral part of the hospital, subject to the hospital conditions of participation
- Isn’t separately Medicare-enrolled or Medicare-certified or subject to the ASC coverage conditions
Each ASC must comply with the CfCs, which are health and safety regulations. Each condition has several standards. In general, ASCs must meet established standards for:
- Processes to remain compliant with state licensure laws
- A governing body and management
- Safe surgical procedures
- Quality assessment and performance improvement
- A safe and sanitary environment to protect patients’ health and safety
- Medical staffing
- Nursing services
- Complete, comprehensive, and accurate medical records
- Pharmaceutical services
- Lab and radiology services
- Patients’ rights
- Infection prevention and control to minimize infections and communicable diseases
- Patient admission, assessment, and discharge
- Emergency preparedness
The ASC payment system establishes payment rates for eligible ASC procedures.
ASCs get a single payment for each procedure we cover, including these facility items and services:
- Nursing, technician, and related services
- Facility use for surgical procedures
- Clinical Laboratory Improvement Amendments-waived tests
- Drugs and biologicals (when we make no separate Outpatient Prospective Payment System (OPPS) payment)
- Medical and surgical supplies not on pass-through status
- Equipment
- Surgical dressings
- Implantable prosthetic devices, including intraocular lenses and related accessories and supplies not on pass-through status
- Implanted DME and related accessories and supplies not on pass-through status
- Splints, casts, and related devices
- Radiology services and diagnostic tests or interpretive services for which we don’t allow separate payment under the OPPS
- Administrative, record keeping, and housekeeping items and services
- Anesthesia administration and monitoring supplies and equipment
- Anesthetist services supervised by the operating surgeon
- Blood, blood plasma, and platelets, except when the blood deductible applies
We pay separately for ASC ancillary services that are integral to a surgical procedure we cover. Covered ancillary items and services, which can be provided immediately before, during, or after the procedure, include:
- OPPS drugs and biologicals paid separately
- OPPS radiology services and diagnostic tests paid separately
- Groups of skin substitute supply products that are separately payable under the OPPS
- Brachytherapy sources
- Certain implantable items with OPPS pass-through status
- Corneal tissue acquisition
- Non-opioid pain management drugs, biologicals, and medical devices
42 CFR 416.164(c) lists ASC items and services we don’t cover.
We cover surgical procedures that meet 42 CFR 416.166(a) – (e) requirements.
We evaluate the ASC Covered Procedures List (CPL) each year to determine whether we’ll add or remove procedures. For CY 2026, we finalized our proposal to revise the ASC CPL criteria to modify the general standard criteria and to eliminate 5 of the general exclusion criteria, moving them into a new section as nonbinding physician considerations for patient safety. As a result of these criteria changes, we added 289 procedures to the ASC CPL. Additionally, we added 271 codes to the ASC CPL that were removed from the Inpatient Only List for CY 2026.
Certified providers or suppliers may provide and bill for other services in ASCs that aren’t considered ASC services. ASCs should submit claims on the CMS-1500 or the electronic equivalent, 837P.
We charge the ASC patient their 20% coinsurance payment after they meet their yearly Medicare Part B deductible. We waive coinsurance and deductibles for certain preventive services.
Under the ASC payment system, we pay prospectively determined amounts for services connected to covered surgical procedures the ASC provides to patients. CPT and HCPCS codes identify the surgical procedures and ancillary services we cover.
Using the OPPS Ambulatory Payment Classification relative payment weights, we annually revise the ASC relative payment weights for most covered surgical procedures in the ASC payment system, since ASCs don’t submit cost reports. We then scale those ASC relative weights for the ASC payment system to ensure budget neutrality. For device-intensive procedures, we set the device amounts of these surgical procedures equal to the device amount under the OPPS (based on the standard ASC rate setting methodology). The device-related portion of device-intensive procedure isn’t scaled. To calculate the ASC payment rates for ASC-covered surgical procedures with ASC relative weights, we multiply the ASC conversion factor (CF) by the ASC relative payment weight. Covered surgical procedures that don’t have ASC relative weights are those paid at the Physician Fee Schedule (PFS) rate. To calculate the ASC payment rates for procedures paid at the PFS rate, we multiply the PFS CF by the PFS non-facility practice expense relative value unit (PE RVU).
We scale ASC relative payment weights for ASC-covered surgical procedures, covered ancillary radiology services, and certain diagnostic tests.
The weight scalar is the ratio of the current CY expenditures to the upcoming CY total expenditures. We apply it to the upcoming CY relative payment weights to maintain budget neutrality.
We annually adjust the CF for budget neutrality by removing the total expenditures impact from changes in wage index values for the upcoming year compared with the current year through a wage index scalar.
Since CY 2019, we’ve updated the ASC CF using the productivity-adjusted hospital market basket update factor.
For CY 2026, we finalized a 2.6% update factor to ASC payment rates for ASCs meeting the quality reporting requirements. We base this update on the final hospital market basket update of 3.3%, reduced by a 0.7 percentage point productivity adjustment.
We apply a 0.6% hospital market basket update factor to the CY 2025 ASC CF for ASCs not meeting the quality reporting requirements.
For each procedure or service, ASCs get the lesser of the actual charge or the ASC payment rate.
We make a geographic payment adjustment using modified pre-floor and pre-reclassified inpatient hospital wage index values. Any reduction in a geographic area’s pre-floor and pre-reclassified inpatient hospital wage index values is capped at a 5% reduction. The ASC wage index value is applied to the 50% labor-related factor for covered surgical procedures and certain covered ancillary services. We make an additional adjustment when the ASC provides multiple surgical procedures in the same encounter or when ASC personnel stop procedures before starting anesthesia.
| Surgical Procedure or Ancillary Service | Payment Method |
|---|---|
| Procedures CMS classifies as office-based and performed in a physician’s office at least 50% of the time | Paid at the lower of the ASC rate or the non-facility PE RVU amount of the relevant year’s PFS |
| Device-intensive procedures (ASC-covered surgical procedures which require an insertable or implantable device and the estimated device offset percentage is greater than 30% of the HCPCS code’s geometric mean cost based on the most recent data) | Paid with the procedure’s device-related portion and a non-device-related portion, calculated according to the standard rate-setting method |
| Separately payable facility costs for covered ancillary radiology services | Paid at the lower of the ASC rate or the technical component or non-facility PE RVU amount of the same year’s PFS (whichever applies) |
| Separately payable OPPS drugs, biologicals, and radiopharmaceuticals (except non-opioid pain management drugs or biologicals) | Paid at the same amount as OPPS |
| Non-opioid pain management drugs or biologicals when provided in the ASC setting | Separately paid, generally at the average sales price plus 6%, and subject to a payment limitation (an estimated volume weighted average of 18% of the payment rates of the top 5 primary procedures by volume into which a non-opioid treatment for pain relief would have its payment packaged) |
| Non-opioid pain management devices | Separately paid at the amount of the provider’s charges for the device, adjusted to cost, and subject to a payment limitation (an estimated volume weighted average of 18% of the payment rates of the top 5 primary procedures by volume into which a non-opioid treatment for pain relief would have its payment packaged) |
| Brachytherapy sources | Paid the same as OPPS rates if a prospective OPPS rate is available (otherwise, we pay at contractor-priced rates); we don’t adjust payment for geographic wage differences |
| Skin substitute products | Paid the same amount as the OPPS; we don’t adjust payment for geographic wage differences |
| Low-volume device-intensive procedures | Paid at the ASC rate (including device-intensive adjustments), not to exceed the procedure’s OPPS payment rate |
| Primary surgical procedure and packaged add-on code combinations that are eligible for complexity adjustments under the OPPS and performed in the ASC setting | Paid at the ASC rate through C codes that correspond to each unique code combination, calculated on the basis of the OPPS complexity-adjusted rate |
ASC Payment explains final ASC payment policies, the ASC CPL and payment rates, and the ASC payment system quarterly addenda updates.
The ASC Quality Reporting (ASCQR) Program is a pay-for-reporting quality program for the ASC setting. It publicly reports on quality-of-care measures, quality improvement, and information transparency to promote better health outcomes for Medicare patients. Facilities can also view their data and compare their performance with other outpatient settings’ through the ASC Compare tool on Quality Reporting Center.
Eligible ASCs that don’t report their quality data according to program requirements get a reduction of 2% from their annual fee schedule update in the next payment determination year.
Find more information about the ASCQR Program on QualityNet and in 42 CFR 416 Subpart H.
Resources
DMEPOS Fee Schedule
What’s Changed?
Note: No substantive content updates.
Medicare Part B (medical insurance) covers various DMEPOS items and services when a qualified provider prescribes them and documents medical necessity that meets Medicare coverage requirements.
We limit our DME coverage to medically necessary items and services used in a Medicare patient’s home, including an institution serving as the patient’s home. A hospital or skilled nursing facility isn’t considered a patient’s home.
We pay for DMEPOS items and services through either:
- A fee schedule. We update the schedule in January (and in April, July, and October, if needed). We pay 80% of the supplier’s actual charge or the fee schedule amount, whichever is lower. The patient pays the remaining 20% coinsurance after they’ve paid their deductible.
- The Competitive Bidding Program (CBP), which requires bidders to compete for supplier contracts that provide DMEPOS items throughout a competitive bidding area. Contract suppliers must accept assignment on all claims for bid items, and we pay a single amount. A temporary gap period in the DMEPOS CBP started on January 1, 2024. During the temporary gap period, any Medicare-enrolled DMEPOS supplier may provide a DMEPOS item, including items that were formerly included in the CBP.
We pay for certain DMEPOS items and services on a fee schedule based on sections 1834(a), (h), and (i) of the Social Security Act and 42 CFR 414.102 for parenteral and enteral nutrition, splints, casts, and intraocular lenses inserted at a physician’s office.
The fee schedule files contain certain HCPCS codes that are subject to fee schedule adjustments using payment information from the CBP. We determine the payments for these items under the CBP and adjust the fee schedule amounts for the items using payment information from the program when they’re provided outside the program (in non-competitive bidding areas).
The fee schedule adjustment methodologies and regulations at 42 CFR 414.210(g) consider the differences in the costs of items from competitive bidding areas versus non-competitive bidding areas. The fee schedule files also include codes for items and services that aren’t subject to the program or fee schedule adjustments.
The DMEPOS Fee Schedule: CY 2026 Update has more information on DMEPOS fee schedule amounts and adjustments.
For more payment guidance, see:
We’ve streamlined regulatory requirements to help simplify DMEPOS payment requirements and reduce provider and supplier burden through the Master List of DMEPOS Items Potentially Subject to Conditions of Payment. The Master List is a library of Fee-for-Service DMEPOS codes that are flagged as potential vulnerabilities.
Providers and suppliers don’t need to act unless an item on the Master List also appears on 1 or both of these lists:
Some DMEPOS items that are frequently subject to unnecessary use require prior authorization as a condition of payment, and these items are on the Required Prior Authorization List. The prior authorization process ensures you meet all coverage, coding, and clinical documentation requirements before you provide the item to the patient and submit the claim.
Starting January 1, 2026, we’ll offer suppliers an exemption from required prior authorization if they achieve an approval rate of at least 90% of prior authorization requests during an initial or periodic assessment. You can decline this exemption. If we withdraw the exemption because you don’t continue to meet the 90% approval rate, we’ll notify you at least 60 days before the effective date.
Prior Authorization and Pre-Claim Review Initiatives has more information.
Along with annual updates in January, we sometimes update fee schedules in April, July, and October when we:
- Add new items (HCPCS codes)
- Make necessary fee schedule corrections
- Apply statute or regulation changes as outlined in the Medicare Claims Processing Manual, Chapter 23, section 60
Section 1834(a)(14)(L) of the Social Security Act updates certain DMEPOS fee schedule amounts by the percentage increase in the Consumer Price Index for all Urban Consumers (CPI-U) (U.S. city average) for the 12-month period ending June 30 of the previous year.
We base this adjustment on the economy-wide productivity change equal to the 10-year moving average of changes in annual economy-wide private non-farm business total factor productivity (TFP).
For 2026, the TFP adjustment is 0.7%, and the CPI-U percentage increase is 2.7%. We reduced the 2.7% increase in the CPI-U by the 0.7% increase in the TFP, resulting in a net 2% increase update factor.
We require documentation indicating that the patient confirmed the need for the refill within the 30-day period before the end of the current supply. Delivery of DMEPOS items (in other words, the date of service) can’t be sooner than 10 calendar days before the expected end of the current supply.
Resources
Home Health Prospective Payment System & Coverage
What’s Changed?
Note: No substantive content updates.
Medicare pays home health agencies (HHAs) a national, standardized 30-day period payment rate that includes a bundle of home health services, including skilled nursing, physical therapy, speech-language pathology, occupational therapy, medical social services, and home health aides. Periods of care must meet a certain threshold of home health visits. We adjust the payment rate for case-mix and geographic differences in wages. We pay a per-visit payment rate for the care provided during 30-day periods that don’t meet the per-visit threshold. The Patient-Driven Groupings Model (PDGM) bases payments on 30-day periods and relies on clinical characteristics and other Medicare patient information to place home health care periods into meaningful payment categories. The 30-day period payment may also include some medical supplies.
We cover home health services if:
- The patient meets the criteria outlined in:
- Medicare Benefit Policy Manual, Chapter 7, section 30
- 42 CFR 409.42
- Sections 1814(a)(2)(C) and 1835(a)(2)(A) of the Social Security Act
- The HHA providing the services has a valid Medicare Program agreement to participate
- The HHA submits a covered-services claim
- Services provided aren’t otherwise excluded from covered services
Patient Eligibility
Patients are eligible for Medicare home health services if they meet all these criteria:
- Are enrolled in Medicare Part A or B
- Need skilled nursing (SN) care (on an intermittent basis), physical therapy (PT), or speech-language pathology (SLP) services, or continue to need occupational therapy (OT)
- Are under a physician’s or allowed practitioner’s care
- Get services under a home health plan of care (POC) that a physician or allowed practitioner established and periodically reviews
- Are confined to home (homebound)
- Had a face-to-face encounter with a physician, nurse practitioner, clinical nurse specialist, physician assistant, or certified nurse-midwife that was related to the primary reason the patient requires home health services
Occupational therapists can complete the initial and comprehensive patient assessments only when the physician or allowed practitioner orders a therapy service with another rehabilitation therapy service (SLP or PT).
We consider a patient confined to home (homebound) if they meet these criteria:
Criterion 1
The patient must meet 1 of these requirements:
- Because of illness or injury, needs supportive devices like crutches, canes, wheelchairs, or walkers; uses special transportation; or requires another person’s help to leave their home
- Has a condition in which leaving their home isn’t medically advised
If the patient meets 1 of the requirements in Criterion 1, they must also meet both requirements in Criterion 2:
Criterion 2
The patient must also meet both requirements:
- The patient normally can’t leave home
- Leaving home requires a considerable and taxing effort
We consider a person confined to home (homebound) if they don’t leave their home often, or if they leave only for a short time for health care services, religious services, adult day care, or other unique or infrequent events (for example, funerals, graduations, barber or hairdresser services).
Confined to home (homebound) examples:
- A person who’s blind or has dementia and needs help to leave home
- A patient who returns home after surgery and whom a physician or allowed practitioner has restricted to specific limited activities (like getting out of bed only for a specified length of time or taking the stairs only once a day)
- A person with a mental health disorder who refuses to leave home or whose physician or allowed practitioner considers it unsafe to leave home unattended, even if they have no physical limitations
Skilled Therapy
We cover skilled therapy services (PT, SLP, and OT) to maintain the patient’s current condition or to prevent or slow further deterioration. Services must be:
- Performed safely and effectively by, or under the supervision of, a skilled therapist
- Consistent with the nature and severity of the illness or injury and the patient’s particular medical needs; the amount, frequency, and duration of services must be reasonable
- Specific, safe, and effective treatment for the patient’s condition
- Reassessed at least once every 30 days by a qualified therapist from each involved therapy discipline to compare the patient’s resultant measurement against the prior assessment measurement
- Documented in the clinical record to reflect the need for the skilled care provided
Skilled Nursing
We cover SN care (other than only venipuncture for getting a blood sample) when the patient:
- Needs the specialized judgment, knowledge, and skills of a registered nurse (RN) or licensed practical (vocational) nurse (LPN) (if regulations allow)
- Requires SN services to maintain their current condition or prevent or slow further deterioration
We cover skilled nursing based on the patient’s need for skilled care rather than their potential for improvement. We don’t consider a service to be a skilled nursing service merely because it’s performed by or under the supervision of a nurse. However, in some cases, the patient’s condition may cause a service that we’d ordinarily consider unskilled to be considered a skilled nursing service.
Intermittent Skilled Nursing Care
We define intermittent SN care as care patients need for fewer than 7 days each week or less than 8 hours each day for periods of 21 days or less (with extensions in exceptional circumstances requiring more limited and predictable care).
To meet intermittent SN care requirements, patients must need a medically predictable recurring SN service, which typically occurs when a patient needs an SN service at least once every 60 days. The exception to the intermittent requirement is daily SN services for patients living with diabetes who are unable to administer their insulin, when they don’t have an able and willing caregiver.
Home Health Aide
We cover home health aide services if a patient qualifies for the home health benefit. These services can include:
- Personal care
- Help with activities that directly support skilled therapy services but don’t require the skills of a therapist, such as routine maintenance exercises and repetitive practice of functional communication skills
- Simple dressing changes
- Assistance with medications that are ordinarily self-administered and don’t require the skills of a licensed nurse
- Prosthetic or orthotic device personal care
To provide these services, a home health aide must meet all these criteria:
- Meet the training and evaluation requirements in 42 CFR 484.80(a); training requirements may vary by state
- Provide hands-on, personal care or services that help treat a patient’s illness or injury or maintain a patient’s health
- Perform only tasks allowed under state law
Orders for home health aide services must show how often patients need these services. A registered nurse or other skilled professional must supervise the home health aide on-site at least every 14 days if the patient gets SN, PT, OT, or SLP services. In rare instances outside the HHA’s control, we allow 1 virtual supervisory visit per 60-day episode of care, which HHAs must document in the patient’s medical record.
Medical Social Services
We cover medical social services when all these criteria are met:
- The patient is eligible for the home health benefit
- The POC explains why only a qualified medical social worker, or social work assistant under a qualified medical social worker’s supervision, can safely and effectively provide services the patient needs
- Services resolve social or emotional problems that complicate a patient’s medical condition or recovery rate
Telehealth & Remote Patient Monitoring
The POC must indicate services using telecommunication technology, which can include:
- Remote patient monitoring, defined as collecting physiologic data (for example, electrocardiogram, blood pressure, glucose monitoring) that’s digitally stored or transmitted by the patient or caregivers, or both, to the HHAs
- Teletypewriter (TTY)
- Telehealth, defined as real-time interaction between the patient and clinician via 2-way audio-video technology
Telecommunication technology services aren’t separately billable and can’t be counted as a visit for payment or eligibility requirements. Visits to a patient’s home solely to supply, connect, or train them on equipment, without providing another skilled service, aren’t separately billable.
Telecommunication technology services must meet patient-specific needs as identified in the comprehensive assessment. HHAs can’t substitute telecommunications or audio-only technology for a home visit as part of the POC or for patient eligibility or payment purposes.
See Telehealth & Remote Patient Monitoring for more information.
CMS Telehealth helps physicians, practices, and health systems navigate changes to Medicare telehealth policy.
The productivity-adjusted CY 2026 home health market basket update is 2.4% (3.2% market basket increase, reduced by a 0.8 percentage point productivity adjustment).
We applied a remaining permanent adjustment of -1.023% to the CY 2026 home health prospective payment rate to account for the impact of implementing the PDGM. We also applied a -3% temporary adjustment to the CY 2026 base payment rate.
PDGM & Home Health Resource Groups
The PDGM case-mix methodology bases 30-day period payment rates on the patient’s clinical characteristics and resource needs. It assigns each 30-day period to 1 of 432 case-mix groups called home health resource groups.
We base case-mix payment on these groups, and each group’s case-mix weight reflects predicted mean group cost relative to the overall average across all groups.
We apply changes to the PDGM case-mix weights in a budget-neutral manner by multiplying the CY 2026 national standardized 30-day period payment rate by a case-mix budget-neutrality factor. The final CY 2026 case-mix budget-neutrality factor is 1.0052.
We base the national, standardized 30-day period payment for case-mix on the patient’s condition, care needs, and area wage differences.
Adjustments to the 30-Day Period Payment Rate
Case-Mix Adjustments
We use a case-mix methodology that adjusts the 30-day period payment rate based on the patient’s characteristics and their corresponding resource needs.
We put the 30-day periods into different subgroups for each of these categories:
- Admission Source
- Community
- Institutional (acute hospital, inpatient rehabilitation facility, skilled nursing facility, long-term care hospital, inpatient psychiatric facility)
- 30-Day Period Timing
- Early (first 30-day care period)
- Late (all subsequent 30-day care periods, unless there’s a gap of more than 60 days between the end of 1 care period and the start of another)
- Clinical Grouping
- Musculoskeletal Rehabilitation
- Neuro/Stroke Rehabilitation
- Wounds: Post-Op Wound Aftercare and Skin/Non-Surgical Wound Care
- Behavioral Health Care
- Complex Nursing Interventions
- Medication Management, Teaching, and Assessment (MMTA):
- MMTA — Surgical Aftercare
- MMTA — Cardiac/Circulatory
- MMTA — Endocrine
- MMTA — Gastrointestinal Tract/Genitourinary System
- MMTA — Infectious Disease/Neoplasms/Blood-forming Diseases
- MMTA — Respiratory
- MMTA — Other
- Comorbidity Adjustment Based on Reported Secondary Diagnoses
- None
- Low
- High
- Functional Impairment Level from OASIS Assessment (based on 30-day care period)
- Low
- Medium
- High
Labor Adjustments
The labor portion bases each 30-day period payment adjustment on wage levels and wage-related costs of providing patient home health care in different geographic areas.
We cap decreases to the home health wage index in a geographic area so the wage index isn’t less than 95% of the wage index in that area in the previous CY. We apply this 5% cap on negative wage index changes in a budget-neutral manner using wage index budget-neutrality factors.
Continuous 60-Day Recertifications
The Home Health Prospective Payment System (PPS) allows continuous 60-day patient recertification when the patient remains eligible.
Medicare conditions of participation require a recertification assessment during the last 5 days of each certification period (for example, during the initial 60-day certification period, complete the recertification visit on days 56–60).
Submitting the Notice of Admission
HHAs must submit a one-time Notice of Admission (NOA) to their Medicare Administrative Contractor (MAC) within 5 days after the start-of-care date to establish that the patient is under a home health period of care that covers all 30-day periods until the patient is discharged from home health services.
HHAs may submit the NOA under these conditions:
- The certifying physician’s or allowed practitioner’s written or verbal order meets the requirements in 42 CFR 409.43(d) and 42 CFR 484.60(b)
- The initial visit happened within the 60-day certification period, and the patient was admitted to home health care
We may waive the consequences of not submitting an NOA on time if we determine the HHA encountered a circumstance that’s exceptional and qualifies for the waiver.
Plan of Care
The certifying physician or allowed practitioner must periodically review the POC, which must include:
- The services meeting the patient-specific needs identified in the comprehensive assessment
- The responsible disciplines and the frequency and duration of all visits
- The individualized standards listed in 42 CFR 484.60(a) that establish the need for services
- Telehealth, remote patient monitoring, or other services provided through telecommunications technology
If the signed POC isn’t available at the time of NOA submission, the HHA must base the submission on 1 of these:
- A physician’s or allowed practitioner’s verbal order that:
- Is recorded in the POC
- Describes the patient’s condition and the services the HHA provides
- Has a responsible registered nurse’s or qualified therapist’s (as defined in 42 CFR 484.115) signed and dated attestation for providing or supervising services ordered in the POC
- Is copied into the POC, which is immediately submitted to the physician or allowed practitioner
- A referral with a detailed order for services the HHA provides that the physician or allowed practitioner signed and dated
Other POC requirements include:
- A physician or allowed practitioner who meets the certification and recertification requirements in 42 CFR 424.22 must sign and date the POC or any changes in the POC before submitting the claim for each 30-day period
- The physician or allowed practitioner must review the POC at least every 60 days or more frequently if these apply:
- The patient wants a transfer
- There’s a change in the patient’s condition
- The patient is discharged with goals met or no expectation they’ll need home health care and then returns to home health care within 60 days
- The POC is terminated if the patient doesn’t get at least 1 covered SN, PT, SLP, or OT visit in a 60-day period unless the physician or allowed practitioner documents that the interval without this care is appropriate for treating the patient
Low Utilization Payment Adjustment
We make per-visit payments, called low utilization payment adjustment (LUPA) payments, for 30-day periods with a number of visits below the case-mix group’s threshold instead of paying the case-mix adjusted 30-day period payment amount. We updated the CY 2026 LUPA thresholds using CY 2024 data.
Submit appropriate claims and supporting documentation for us to apply the LUPA threshold. Documentation must show the patient’s condition and care needs or the case-mix assignment.
Note: We may adjust a home health claim based on other claims a provider may or may not bill. Those claims could affect the Common Working File and PPS code already billed or paid.
Partial-Period Payments
We adjust payments if a patient has an intervening event, which we define as:
- A patient choosing to transfer from 1 HHA to another
- An HHA discharging a patient with goals met or no expectation to return and then readmitting them within 30 days of the original 30-day period start date
We prorate case-mix adjusted payments for 30-day periods of that type according to the length of the 30-day period ending in a transfer or discharge and readmission, resulting in partial-period payment.
We recognize a discharge and return to the same HHA during the 30-day period only when a patient reaches treatment goals in the original home health POC.
Terminate the original home health POC if you anticipate that the patient won’t need home health services for the rest of the 30-day period.
We base the partial-period payment on how long the patient was under the original HHA’s POC before an intervening event (from the first to the last billable service date). We compare the number of days in that period with the full 30-day period to find the proportion of care provided. We then multiply that proportion by the original case-mix and wage index to determine the partial-period payment adjustment.
Partial-period payment adjustments don’t apply for transfers among HHAs of common ownership. We consider those situations services that the receiving HHA with ownership interest provides under arrangement on behalf of the originating HHA until the end of the 30-day period.
Outlier Payments
We allow outlier payments when a 30-day period has unusually large, costly patient home health care needs. We add these outlier payments to the regular 30-day period case-mix and wage-adjusted period payments when estimated costs exceed a threshold amount for each home health resource group.
You can calculate the amount of the outlier payment using steps 1–6 in the Medicare Benefit Policy Manual, Chapter 7, section 10.8.
Note: In CY 2026, the fixed-dollar loss ratio is 0.37 to make sure aggregate outlier payments don’t exceed 2.5% of total aggregate payments.
Consolidated Billing Requirements
We include all HHA services and supplies in the Home Health PPS 30-day period payment rate for patients under a home health POC except:
- Certain covered injectable osteoporosis drugs when patients meet specific criteria
- DME, including home infusion drugs and related services
- Negative pressure wound therapy (NPWT) disposable devices
Provide all other covered home health services directly or under arrangement, which is when an outside supplier provides services under contract and looks to the HHA for payment. The HHA bills the MAC for covered home health services.
We subject certain home health services and supplies to the consolidated billing Home Health PPS requirements, and you should bill them with the 30-day period payment rate.
Physicians and allowed practitioners, including clinical nurse specialists, physician assistants, and nurse practitioners, can certify and recertify eligibility, order home health services, and review the POC. Certifying physicians or allowed practitioners must authorize physicians or NPPs to care for the patients in their absence. These physicians or NPPs don’t have to be in the same group practice as the certifying physician or allowed practitioner.
For more information:
- Medicare Benefit Policy Manual, Chapter 7, section 30.5.1 explains certifying patient eligibility for Medicare home health services
- Medicare Benefit Policy Manual, Chapter 7, section 30.5.1.1 discusses the home health face-to-face encounter
- Medicare Benefit Policy Manual, Chapter 7, section 30.5.4 outlines billing for certification and recertification
- Medicare General Information, Eligibility, and Entitlement Manual, Chapter 4, section 30 discusses certification and recertification by physicians and allowed practitioners
The Home Health Quality Reporting Program (HH QRP) is a pay-for-reporting quality program for the home health setting. It uses public reporting of quality-of-care measurements, quality improvements, and information transparency to promote better health outcomes for Medicare patients.
HHAs must submit admission and discharge OASIS assessments for at least 90% of patients with care episodes occurring during the reporting period. Report data using OASIS and the Home Health Care CAHPS Survey. HHAs use additional quality measures on each claim.
For HHAs that don’t submit the required quality data for CY 2026, the home health payment update is 0.4% (2.4% minus 2 percentage points).
HHAs qualify for the full home health update factor by submitting required quality data for specific quality-of-care measures. Home Health Quality Measures has more information.
HHAs may qualify for an HH QRP reconsideration and an extension or exemption.
The iQIES, which includes survey and certification functions, replaces and consolidates the QIES, CASPER, and ASPEN legacy systems.
Resources
Hospice Payment System & Coverage
What’s Changed?
- Added information about reporting face-to-face encounters through telehealth
- Added information about the mandatory election statement addendum
- Added information about reelecting the hospice benefit after revocation
- Updated the FY 2027 payment rates and cap amount
- Updated the accounting years in which we use the hospice payment update percentage for the hospice aggregate cap
Substantive content changes are in dark red.
The Medicare hospice benefit covers palliative services for Medicare patients who elect hospice. To get these services, patients must:
- Be eligible for Medicare Part A
- Be certified as terminally ill with a medical prognosis of 6 months or less to live if the illness runs its normal course
- Use a Medicare-approved hospice program
- Sign a hospice election statement
- Waive all coverage rights for the terminal illness and related conditions, unless the hospice arranges or delivers the care
The Medicare hospice benefit includes these services to relieve pain or symptoms and manage terminal illness:
- Physician services
- Nursing care, including nurse practitioner (NP) services
- Medical equipment
- Medical supplies
- Drugs and biologicals for pain control and symptom management
- Home health aide and homemaker services
- Physical therapy, occupational therapy, or speech-language pathology services
- Medical social services under a physician’s direction
- Counseling—including but not limited to bereavement, dietary, and spiritual counseling—for the purpose of helping the patient and those caring for the patient to adjust to the patient’s approaching death
- Individual and family grief and loss counseling before and up to 1 year after the patient’s death
- Short-term inpatient pain control, symptom management, and respite care
- Other services specified in the patient’s plan of care (POC) as reasonable and necessary for the palliation and management of the terminal illness and related conditions
In exceptional circumstances, we may pay benefits unrelated to a terminal illness and related conditions. The hospice should provide nearly all care to a patient who has elected hospice.
When a patient elects hospice care, we don’t pay for:
- Hospice care from a hospice other than the one the patient designates, unless provided under arrangement by the designated hospice
- Room and board, unless the hospice arranges short-term inpatient care
- Hospital or other inpatient facility services; outpatient services, like in an emergency department; or ambulance transportation, unless the hospice arranges these services or they’re unrelated to the patient’s terminal illness and related conditions
Note: When you admit patients, inform them in writing that their care is subject to Quality Improvement Organization (QIO) review and discuss potential review results.
A physician, NP, or physician assistant (PA) who’s an employee of, or under contract with, a rural health clinic (RHC) or federally qualified health center (FQHC) can provide hospice attending physician services to a hospice patient. The RHC or FQHC can bill and get paid for these services under the RHC All-Inclusive Rate (AIR) or FQHC Prospective Payment System (PPS), respectively.
To get paid under the RHC AIR or FQHC PPS, the RHC or FQHC must report the GV modifier (attending physician not employed or paid under arrangement by the patient’s hospice provider) when a physician, NP, or PA employed by, or under contract with, an RHC or FQHC provides hospice services to a hospice patient.
Medicare Benefit Policy Manual, Chapter 13, section 210 and Medicare Claims Processing Manual, Chapter 9, section 60.6 have more information.
Patients who are dually eligible veterans and live at home in their community may elect hospice services and have them paid for under the Medicare hospice benefit. Sections 1853(c) and 1814(d) of the Social Security Act and Medicare Benefit Policy Manual, Chapter 9, section 60 have more information.
42 CFR 418.52 requires you to give the patient or representative verbal and written notice of their rights and responsibilities during their initial assessment before you provide care.
42 CFR 418.54 requires you to complete a patient-specific comprehensive assessment that identifies the patient’s need for:
- Hospice care and services
- Physical, emotional, psychosocial, and spiritual care, including a bereavement assessment for the patient’s family and other people
42 CFR 418.56(c) requires the POC to list all services necessary for the palliation and management of the terminal illness and related conditions. The POC must include:
- Interventions for pain and symptom management
- Details about the scope and frequency of services necessary to meet specific patient and family needs
- Measurable outcomes expected from implementing and coordinating the POC
- Patient treatment and drug needs
- Patient medical supplies and appliance needs
- The interdisciplinary group’s (IDG’s) documentation of the patient’s or representative’s level of understanding, involvement, and agreement with the POC
Coordination of Services
To minimize fragmented care and improve quality of life, 42 CFR 418.56(e) requires that the hospice develop and maintain a communication and integration system among all providers delivering care to terminally ill patients. Clearly identify related and unrelated conditions and who’s responsible for delivering services for those conditions. Share this information with non-hospice providers delivering services unrelated to the terminal illness.
Hospice Aide Training & Evaluation
Hospice aides deliver a significant portion of direct care. Verify that aides meet the training requirements and have demonstrated competency in providing appropriate care. You may observe and assess an aide’s skill competencies with a patient or in a pseudo-patient simulation as defined in 42 CFR 418.3. If the hospice verifies an area of concern during the on-site visit, it must conduct—and the hospice aide must complete—a competency evaluation of the deficient skill and all related skills.
The hospice’s medical director (or designee), or the physician member of the hospice IDG, and the patient’s designated attending physician (if they have one) must certify that the patient is terminally ill no later than 2 calendar days after the patient starts hospice care for their initial 90-day coverage period.
When the patient elects hospice, they may designate an attending physician, who will have the most significant role in determining and delivering the patient’s medical care. The patient may select:
- A doctor of medicine (MD)
- A doctor of osteopathy (DO)
- An NP
- A PA
Only an MD or a DO can certify or recertify that the patient is terminally ill. If a patient’s attending physician is an NP or a PA, the hospice medical director, the physician designee, or the hospice IDG physician member must be the one to certify the patient as terminally ill.
If a patient or their representative wants to change attending physicians, they must file a signed statement with the hospice indicating the change.
When a patient chooses hospice care, the hospice must identify an IDG to manage their care. The IDG must include, but isn’t limited to, people who are qualified and competent to practice in these professional roles:
- MD or DO (who’s an employee of or under contract with the hospice)
- Registered nurse (RN)
- Social worker, marriage and family therapist, or mental health counselor
- Pastoral or other counselor
The initial election period certification lasts 90 days. After the initial period, the patient gets another 90-day period and unlimited 60-day election periods. An MD or a DO must certify or recertify the patient as terminally ill each election period.
A hospice must get written certification and document it in the patient’s clinical record before submitting a claim to its Medicare Administrative Contractor (MAC). Complete certifications include:
- A statement certifying the patient is terminally ill with 6 months or less to live if the terminal illness runs its normal course
- Specific clinical findings and documentation supporting a life expectancy of 6 months or less
- A certified physician’s brief narrative explaining clinical findings supporting a life expectancy of 6 months or less
- The certifying physician’s signature (or certifying physicians’ signatures, as appropriate), a certification signature date, and benefit period dates
- Documentation of a physician’s or an NP’s face-to-face visit with the hospice patient to determine continued eligibility for hospice care no more than 30 days before:
- The third benefit period recertification
- Each subsequent benefit period recertification
When you newly admit a patient in their third or a later benefit period, exceptional circumstances may prevent a face-to-face encounter before the benefit period starts.
Starting January 1, 2027, hospices should use HCPCS code G0679 on claims to report face-to-face encounters conducted by a hospice physician or NP for recertification through telecommunications technology.
The hospice physician or NP must document that they had a face-to-face patient encounter. The attestation must:
- Include the face-to-face visit date
- State that the certifying physician got face-to-face clinical findings to determine continued hospice care eligibility
- Include the physician’s or NP’s signature and the date they signed
Note: We allow a signed and dated clinical note to fulfill the attestation requirement. Clearly indicate in the medical record that the face-to-face encounter occurred and include the:
- Date of the visit
- Signature of the practitioner who conducted the face-to-face encounter
- Date of the signature
Hospice Certifying Enrollment
Under section 6405 of the Affordable Care Act, these 2 categories of physicians must be enrolled in Medicare or opted-out of Medicare to get paid for hospice services:
- Hospice medical director or the physician member of the hospice IDG who certifies the patient’s terminal condition
- The patient’s designated attending physician (if they have one) who certifies their terminal condition
Under 42 CFR 418.22(c), for the initial 90-day period, the hospice must get written certification of the patient’s terminal illness from both categories of physicians, if the patient has an attending physician. We allow the hospice to get oral certification if it meets certain exceptions. For subsequent coverage periods, we only require certification by a physician from the first category.
For detailed information on this requirement, refer to the Hospice Certifying Enrollment Q&A.
Procedures for Terminated Hospices
We pay for hospice services up to 30 days after a hospice terminates its Medicare provider agreement. We continue paying for claims that extend beyond a provider’s termination date if both these statements are true:
- The hospice services are provided under a POC established before that date
- The hospice period of care ends within the 30-day period
Patients meeting eligibility requirements must file an election statement, which must:
- Identify the hospice and attending physician providing care. The patient or representative must acknowledge that they chose the attending physician, if applicable. If a patient wants to change attending physicians, they must file a signed statement with the hospice indicating the change.
- Show that the patient or representative understands that hospice is for palliative care rather than curative care.
- Show that the patient or representative understands that they waive certain Medicare services by electing hospice benefits. This includes informing the patient that services unrelated to the terminal illness and related conditions are exceptional and unusual and that the hospice should provide nearly all the care the patient needs. Starting October 1, 2026, you must provide the patient or their representative with an election statement addendum including any conditions, items, services, and drugs that the hospice won’t cover because it determined they were unrelated to the patient’s terminal illness and related conditions. Provide the election statement addendum within the first 5 days of the hospice election effective date. If the patient or their representative refuses to sign the addendum, document on the addendum their refusal to sign and include it in the medical record.
- Show the effective election date, which is the first day of hospice care or a later date but no earlier than the election statement date.
- Provide individual hospice cost-sharing information.
- Provide Beneficiary and Family Centered Care-QIO (BFCC-QIO) information, including the right to immediate advocacy and BFCC-QIO contact information.
- Include the patient’s or representative’s signature.
Note: We require a complete election statement and election statement addendum within the required timeframe containing all required elements as a condition for payment. The addendum isn’t submitted with claims; however, if the addendum wasn’t present within the required timeframe, the claim under review would be denied.
Notice of Election
Hospice providers must file a Notice of Election (NOE) with their MAC through electronic data interchange within 5 calendar days after the hospice election date. If you file the NOE after the 5-day period, you’re liable for services between the hospice election date and the NOE filing date, and you can’t bill the patient for this period.
Note: We make exceptions when the hospice’s inability to file the NOE within 5 calendar days is beyond its control.
Perform an eligibility check immediately before admission so you can reduce potential errors in exception request-related changes to the patient identifier. This confirms that the MBI is active and accurate, since the eligibility inquiry system has an MBI End Date field. If there’s a date in that field, the MBI isn’t valid after that date. Contact the patient or use an MBI lookup tool to get the current MBI to use on the NOE.
Revoking Hospice Election
A patient or representative may revoke hospice election at any time. Revoking a hospice election is the patient’s or representative’s choice, which must be made without undue influence from the hospice provider. To revoke the election, the patient must file a written document with the hospice that includes:
- A signed statement saying they revoke hospice care for the remainder of that election period
- The revocation effective date
The patient gives up their remaining days in that election period, and their previously waived Medicare coverage restarts. A patient may at any time elect to get hospice coverage for any other hospice election periods they’re eligible for. There’s no waiting period for the patient to reelect the hospice benefit after revocation. If the patient continues to meet eligibility requirements, a subsequent election period can start immediately after reelection.
Unless you’ve already submitted a final claim, file a Notice of Termination/Revocation with your MAC within 5 calendar days after either:
- The patient or their representative revokes hospice election
- The hospice discharges the patient alive
Hospice Patient Discharge
A hospice may discharge a hospice patient only if:
- The patient moves out of the hospice service area or transfers to another hospice.
- You find the patient is no longer terminally ill.
- There are extraordinary circumstances, where the hospice can’t continue providing care. These situations include cases in which the safety of the patient or hospice staff is at risk. Before discharging the patient, the hospice must:
- Tell the patient that discharge for cause is under consideration
- Make a serious effort to resolve the issues
- Make sure the discharge isn’t related to the patient’s use of hospice services
- Document the problems and efforts to resolve them in the patient’s medical record
- Notify the MAC and state survey agency and make referrals if necessary
Discharging a patient only to avoid exceeding the cap limit violates these regulations and may cause undue distress and potential harm to terminally ill patients who must find care outside their hospice benefit.
Change of Designated Hospice
A patient can change their designated hospice once each election period with a transfer, which we don’t consider a revocation. To change the designated hospice, the patient must file a signed statement with the hospice where they got care and with the newly designated hospice. The statement must include the:
- Previous hospice name
- New hospice name
- Effective date of change
Notice of Medicare Non-Coverage
We require home health agencies, skilled nursing facilities, hospices, and comprehensive outpatient rehabilitation facilities to provide a Notice of Medicare Non-Coverage (NOMNC) to patients when their Medicare-covered services are ending. The NOMNC tells patients how to request a BFCC-QIO determination and gives them an opportunity to request an expedited determination. A patient gets a Detailed Explanation of Non-Coverage, which gives the specific reasons for ending covered services, only if they ask for an expedited determination.
Even if you don’t provide a service on a given day, we pay for hospice care each day a patient is under hospice election. Payments cover service costs in the patient’s POC, including services directly from, or arranged by, the hospice.
We pay the hospice according to a fee schedule that has 4 levels of care: routine home care, continuous home care, inpatient respite care, and general inpatient care. These levels of care meet different needs the patient and their family have:
- Routine home care, which is when the hospice patient is at home and not getting continuous home care. We pay for routine home care at:
- A higher payment rate for days 1–60
- A lower payment rate for day 61 and beyond
- Continuous home care, which is intended to manage a short-term symptom crisis in the home, involving 8 or more hours of care per day, mostly nursing. The 8 or more hours don’t need to be continuous; you can provide 4 hours in the morning and 4 hours in the evening. When the patient requires fewer than 8 hours of care, we cover the services as routine home care rather than continuous home care.
- Inpatient respite care, which is care in a facility for up to 5 days at a time to give an informal caregiver a break.
- General inpatient care, which is provided in a facility on a short-term basis to manage symptoms that can’t be managed in another setting.
We also pay a service intensity add-on in addition to the routine home care rate for routine home care services during the patient’s last 7 days of life if their care meets these criteria:
- The hospice discharges the patient as deceased
- An RN or social worker provides direct patient care each day
The service intensity add-on payment is the continuous home care hourly payment rate multiplied by the amount of direct patient care an RN or social worker provides during the 7-day period, for a minimum of 15 minutes and up to 4 total hours per day.
For FY 2027, the hospice payment rate update is 2.3% (a 3.2% inpatient hospital market basket increase minus the 0.9 percentage-point productivity adjustment). The FY 2027 hospice cap is $36,174.75.
The base rate for each level of care has a labor share and a non-labor share. To account for local differences in wage levels, we adjust the labor share of the base payment rate by the hospice wage index for the area where you provided services.
| Level of Care | Revised Labor Share | Non-Labor Share |
|---|---|---|
| Routine Home Care | 66% | 34% |
| Continuous Home Care | 75.2% | 24.8% |
| Inpatient Respite Care | 61% | 39% |
| General Inpatient Care | 63.5% | 36.5% |
Wage Index & Cap
We place a permanent 5% cap on any decrease to a geographic area’s wage index from the previous year. This ensures that a geographic area’s wage index doesn’t fall below 95% of its calculation in the previous year, regardless of the reasons for the decline.
Two caps limit the amount and cost of care an individual hospice can provide in a single year:
- The hospice inpatient cap limits the number of inpatient care days that a hospice may provide to no more than 20% of its total patient care days.
- The hospice aggregate cap limits the total actual Medicare payments any individual hospice can get in a cap year to an allowable amount. We limit this amount to the FY cap amount multiplied by the number of patients the hospice serves.
For accounting years that end after September 30, 2016, and before October 1, 2035, we update the aggregate cap amount each year by the hospice payment update percentage (the inpatient hospital market basket percentage increase reduced by the productivity adjustment). After 2035, we’ll base updates to the aggregate cap on the Consumer Price Index for Urban Consumers.
Prescription Drugs or Biologicals
When a patient isn’t a hospice inpatient but is getting routine or continuous home care, you may bill a coinsurance amount for each palliative drug or biological prescription. Coinsurance for each prescription is about 5% of its cost to the hospice. You establish the drug copayment schedule, and the coinsurance for each prescription can’t be more than $5. The patient isn’t liable for any coinsurance for hospice-related drugs or biologicals they get during general inpatient or respite care.
Inpatient Respite Care
For each respite care day, you may bill patients a coinsurance amount equal to 5% of the Medicare respite care day payment. A patient’s respite care coinsurance during a hospice coinsurance period can’t be more than the inpatient hospital deductible for the year the hospice coinsurance period started.
When an enrollee in an MA plan elects hospice, the Medicare FFS Program starts covering most of their services, while the MA plan continues covering certain services.
MA plans must cover all services that Medicare FFS covers, except hospice care. MA enrollees get Medicare FFS hospice benefits and may choose to use a provider outside the MA plan for treatment unrelated to their terminal illness and related conditions, or as their attending physician. When MA enrollees get services unrelated to their terminal illness and related conditions from Medicare FFS providers (not through their MA plan), they’re subject to the 20% coinsurance.
Check with the MA plan for information on a patient’s eligibility, coverage, and payment. Each plan may have different patient out-of-pocket costs and specific rules for getting and billing for services. Follow the plan’s terms and conditions for payment.
MA enrollees needing treatment unrelated to their terminal illness and related conditions may also choose services through their MA plan at the plan cost-sharing level. Benefit costs and coverage may vary by plan. At enrollment and annually thereafter, MA plans must inform enrollees about the availability of Medicare hospice options and about approved hospices in the MA plan’s service area, including:
- Those the MA organization owns, controls, or has a financial interest in
- Whether it’s common practice to refer patients to hospice programs outside the plan’s service area
If a Medicare Advantage (MA) enrollee elects hospice care, Original Medicare covers all hospice care, the attending physician’s services, and care unrelated to the terminal illness. If the MA enrollee revokes their hospice election, they continue to get services through Medicare Fee-for-Service (FFS) (subject to the FFS deductible) until the start of the next month, when they can get services only through their MA plan.
The Hospice Quality Reporting Program (HQRP) provides quality-of-care information so patients can make informed decisions about their health care options. It also encourages facilities and providers to improve their quality of inpatient care by making sure they’re aware of, and reporting on, best practices.
Current Measures has the current quality reporting measures. Public Reporting: Key Dates for Providers has more information.
To meet the hospital quality reporting requirements, hospices must submit data on all quality measures. Eligible hospices that don’t participate in the HQRP in an FY or don’t meet all reporting requirements get a 4% reduction in the annual market basket update.
Hospices may qualify for a quality reporting program extension or exemption.
Hospice Outcomes & Patient Evaluation
The Hospice Outcomes and Patient Evaluation (HOPE) quality reporting tool assesses patient interactions in real time. It can help you understand the patient’s care needs and contribute to the POC. On February 15, 2026, the Quality Improvement and Evaluation System stopped accepting Hospice Item Set records for hospice admissions and discharges that occurred before October 1, 2025, including any corrections. Submit your HOPE records to iQIES.
Consumer Assessment of Healthcare Providers and Systems Survey
The Consumer Assessment of Healthcare Providers and Systems (CAHPS®) Survey is a national survey of family members or friends who cared for a patient who died while under hospice care. Hospices that have 50 or more survey-eligible patient-family caregiver pairs in a reference year must participate in the CAHPS Hospice Survey to get their full annual payment update. We automatically exempt hospices that got their CMS Certification Number after January 1 of the data collection year from participating for that year only.
Resources
Hospital Outpatient Prospective Payment System
What’s Changed?
Note: No substantive content updates.
The Hospital Outpatient Prospective Payment System (OPPS) under section 1833(t) of the Social Security Act pays hospitals and community mental health centers (CMHCs) for services they provide to Medicare patients in an outpatient setting.
Medicare Claims Processing Manual, Chapter 4, section 10.1 discusses services we pay for under OPPS.
42 CFR 419.21 discusses hospital services subject to the OPPS.
The OPPS applies to designated hospital outpatient services in all hospital classes, except:
- Hospitals providing only inpatient Medicare Part B services
- Critical access hospitals (CAHs)
- Indian Health Service (IHS) and Tribal hospitals
- Hospitals in American Samoa, Guam, the Commonwealth of the Northern Mariana Islands, and the U.S. Virgin Islands
- Rural emergency hospitals
- Certain outpatient off-campus provider-based departments (PBDs), which are paid under the Physician Fee Schedule (PFS)
- Maryland hospitals paid under a cost containment waiver according to section 1814(b)(3) of the Social Security Act
We exclude payment for certain outpatient services, like outpatient therapy and screening and diagnostic mammography.
We assign all items and services paid under the OPPS to payment groups called Ambulatory Payment Classifications (APCs), which group together items and services that are similar clinically and in terms of resource use. Under the OPPS, we make APC payments for items and services that hospital outpatient departments provide.
The OPPS assigns a payment status indicator to every HCPCS code, which identifies whether the service payment falls under the OPPS or under another payment system or fee schedule, and, if so, whether it’s paid separately or packaged.
The APC payment rate and calculated copayment apply to each APC service.
Hospitals may get multiple APC payments for patient services on a single day. We discount multiple surgical procedures performed on the same day.
We pay for some items and services separately, including but not limited to:
- Many surgical, diagnostic, and non-surgical therapeutic procedures
- Blood and blood products
- Most clinic and emergency department visits
- Some drugs, biologicals, and radiopharmaceuticals
- Brachytherapy sources
- Corneal tissue acquisition
- Certain preventive services, including vaccine administration
We pay for partial hospitalization on a per diem basis. The payment represents the expected daily facility care costs in hospital outpatient departments and CMHCs. We expanded the existing rate structure to include 2 partial hospitalization program APCs for each provider type—1 for days with 3 services per day and 1 for days with 4 or more services per day.
New Technology APCs
We sometimes assign new services to New Technology APCs when the service can’t be appropriately reported by an existing procedure code assigned to a clinical APC and a new procedure code can’t be appropriately assigned to a clinical APC.
Packaged Costs
Under OPPS, packaged services are items and services that we consider to be an integral part of another primary service paid for under the OPPS. We don’t make a separate payment for packaged services, because we include the cost of packaged items and services in the APC payment for the primary service.
42 CFR 419.2(b) lists some types of packaged items and services. 42 CFR 419.2(c) lists costs we don’t include in the hospital OPPS.
Packaged Drugs, Biologicals & Radiopharmaceuticals
Drugs, biologicals, and therapeutic radiopharmaceuticals below the OPPS drug packaging threshold get packaged payment. In CY 2026, the packaging threshold cost per day for drugs, biologicals, and therapeutic radiopharmaceuticals is $140.
Diagnostic radiopharmaceuticals below the diagnostic radiopharmaceutical packaging threshold get packaged payment. In CY 2026, the packaging threshold cost per day for diagnostic radiopharmaceuticals is $655.
Several categories of nonpass-through drugs, biologicals, and radiopharmaceuticals, regardless of the cost of the products, get packaged payment. Because the products are packaged according to the policies in 42 CFR 419.2(b), we refer to them as policy-packaged drugs, biologicals, and radiopharmaceuticals.
Separately Paid Drugs, Biologicals & Radiopharmaceuticals
Section 1833(t) of the Social Security Act provides for temporary additional payments or transitional pass-through payments. Payments for qualifying or non-packaged drugs, biologicals, and radiopharmaceuticals are generally based on the average sales price (ASP) methodology or other similar payment methodologies.
We determine separately payable medical and surgical rates by multiplying the service’s clinical APC’s prospectively established scaled relative weight by a conversion factor (CF) to get a national unadjusted APC payment rate. The relative APC weight measures the resource service needs based on the APC geometric mean services cost.
The CF translates the scaled relative weights into dollar payment rates. Hospital Outpatient Regulations and Notices has the national unadjusted payment rates and copayments for each HCPCS code in each rulemaking page’s addenda.
To account for geographic price differences, we further adjust the labor portion of the national unadjusted payment rate (60%) by the hospital wage index for the area where we make payment. We don’t adjust the remaining 40%.
For CY 2026, we use the Inpatient Prospective Payment System (IPPS) post-reclassified wage index for urban and rural areas to determine the wage adjustments for both the OPPS payment rate and the standardized copayment amount. Most copayments are 20% of the APC payment rate.
In addition to standard OPPS payments, we pay hospitals:
- Pass-through payments for specific drugs, biologicals, and devices that meet pass-through status criteria (generally, these items are too new to produce payment rate-setting data).
- Outlier payments for individual services that cost hospitals much more than the services’ APC group rates. CMHCs get a separate, capped hospital outlier threshold.
- Transitional outpatient payments for certain cancer hospitals and children’s hospitals.
- An adjustment for certain cancer hospitals.
- Rural adjustments (currently a payment increase of 7.1%) for most services at rural sole community hospitals (SCHs), including essential access community hospitals (EACHs) located in rural areas.
The annual review of APCs and their relative weights considers:
- Changes in hospital and medical practices
- Changes in technology
- Adding new services and removing obsolete services
- New cost data
- Hospital Outpatient Payment Panel recommendations
- Other relevant information
For CY 2026, we increased the OPPS payment rates by a 2.6% outpatient department fee schedule factor, based on the hospital inpatient market basket of 3.3% for inpatient services paid under the hospital IPPS reduced by a 0.7 percentage-point productivity adjustment.
We create other item and service category payment rates through alternative methods, like:
- Separately payable drugs, biologicals, and radiopharmaceuticals
- Brachytherapy sources
- Services assigned to New Technology APCs
We update OPPS payment files quarterly to account for midyear changes, like:
- Adding new pass-through drugs or devices
- Adding new services and procedures to clinical and New Technology APCs
- Removing inpatient only (IPO) list procedures
- Adding new HCPCS codes
- Updating payment rates for separately payable drugs and biologicals based on the most recently available ASP data
We base payment for items and services on the annual scaled relative weights and generally don’t update them quarterly. Medicare Claims Processing Manual, Chapter 4, section 10.3 has more APC payment adjustment information.
We exempt rural SCHs from the site-specific Medicare PFS-equivalent payment for the clinic visit service when an off-campus PBD provides the service.
Revenue Code Selection
Hospital outpatient facilities may determine the most appropriate cost center and revenue code when billing for certain services. If Medicare hasn’t provided specific instructions, hospital outpatient departments should report their charges under the revenue code that will result in the charges being assigned to the same cost center to which the cost of those services are assigned in the cost report. Medicare Claims Processing Manual, Chapter 4, section 20.5 has more information.
If you get claim denials with “Invalid Revenue Code” errors that you believe are due to an outdated edit, contact your MAC.
Outlier Payments
Along with the APC payment, the OPPS provides outlier payments to hospitals to help mitigate the financial risk associated with high-cost and complex procedures, where a very costly service could present a hospital with significant financial loss. Outlier payments are provided on a service basis when the cost of a service exceeds both:
- The APC payment amount multiplier threshold, which is the APC payment amount multiplied by a certain amount
- The APC payment amount plus a fixed-dollar amount threshold, which is the APC payment plus a certain dollar amount
We created the IPO list as part of the initial implementation of the OPPS in 2000. We’re phasing out the IPO list over 3 years, starting with removing 285 mostly musculoskeletal services in CY 2026.
For most hospital and CAH outpatient therapeutic services, the minimum required level of supervision is general supervision for each hospital outpatient service “incident to” a physician’s service.
Under 42 CFR 410.28(e), we allow these non-physician practitioners (NPPs) to supervise cardiac rehabilitation (CR), intensive cardiac rehabilitation (ICR), pulmonary rehabilitation (PR), and diagnostic services as authorized under their scope of practice and applicable state law:
- Nurse practitioners
- Physician assistants
- Clinical nurse specialists
- Certified nurse-midwives
- Certified registered nurse anesthetists
Under 42 CFR 410.28(e)(2)(iii), we permanently allow the physician or NPP to directly supervise CR, ICR, PR, and diagnostic services through audio-video real-time communications technology (excluding audio-only), except for diagnostic services that have a global surgery indicator of 010 or 090.
The 340B Final Remedy rule finalized changes to the calculation of the OPPS CF applicable to non-drug items and services starting in CY 2026. It also codified a 0.5% reduction in the OPPS CF applicable to non-drug items and services, excluding hospitals that enrolled in Medicare after January 1, 2018.
We increased the penalty for some hospitals that don’t comply with the CY 2020 Hospital Price Transparency final rule. We set a maximum civil monetary penalty, $300 per day, for smaller hospitals with a bed count of 30 or less and a $10 per bed per day penalty for hospitals with a bed count greater than 30, not to exceed a maximum of $5,500 daily.
Transformative devices with an FDA Breakthrough Device designation can still qualify for device pass-through payment status even if the substantial clinical improvement criterion doesn’t apply. These devices must have pass-through payment status and must meet the other pass-through status criteria.
Pass-Through Payment Status and New Technology APC has more information on the requirements for device pass-through payment applications.
Request prior authorization for these outpatient department services:
- Blepharoplasty
- Botulinum toxin injections
- Cervical fusion with disc removal
- Facet joint interventions
- Implanted spinal neurostimulators
- Panniculectomy
- Rhinoplasty
- Vein ablation
Medical necessity documentation requirements remain the same. The current standard review time for prior authorization requests for outpatient department services is 7 calendar days.
The Hospital Outpatient Quality Reporting (OQR) Program is a hospital outpatient department pay-for-reporting quality program. Hospitals that don’t report quality data get a 2% reduction in their annual payment update.
Hospitals qualify for the full OPPS update factor by submitting required quality data for specific quality-of-care measures. QualityNet Hospital OQR Program has more information.
Resources
- 2026 OPPS Final Rule
- 42 CFR 419—Prospective Payment System for Hospital Outpatient Department Services
- CMS Hospital Outpatient PPS
- CMS Newsroom: CY 2026 Hospital OPPS and ASC Payment System Final Rule
- Hospital Outpatient Overview
- Prior Authorization for Certain Hospital Outpatient Department Services
Inpatient Psychiatric Facility Prospective Payment System
What’s Changed?
- Included a cap for total outlier payments
- Updated the FY 2027 market basket increase
- Updated the FY 2027 labor-related share (LRS)
- Added the Inpatient Psychiatric Facility Patient Assessment Instrument (IPF-PAI) as part of the IPF Quality Reporting (IPFQR) Program for FY 2028
Substantive content changes are in dark red.
Medicare pays for covered psychiatric services in inpatient psychiatric facilities (IPFs) under a prospective payment system (PPS). IPFs include inpatient psychiatric hospitals and Medicare-certified distinct part psychiatric units in acute care hospitals and critical access hospitals (CAHs).
We cover 90 benefit days per benefit period for patients’ psychiatric conditions. There’s also a 60-day lifetime reserve. The total amount we pay for inpatient psychiatric hospital services over a patient’s lifetime is limited to 190 days. This 190-day lifetime limit applies to psychiatric services in freestanding psychiatric hospitals but not to:
- Inpatient psychiatric services in general hospitals
- Medicare-certified distinct part psychiatric units in acute care hospitals
- CAHs
When a Medicare patient gets covered psychiatric services during an IPF stay, the facility may charge the patient only the appropriate deductible amount.
Medicare Part A pays for services in an IPF only if a physician certifies and recertifies the need. The certification period starts with an inpatient admission order. A certification statement helps us pay only for appropriate services.
Part A pays for IPF services if the admitting physician:
- Certifies, at the time of admission or as soon as possible, that the patient needs inpatient psychiatric services that are reasonably expected to improve the patient’s condition, or for aid in diagnostic study. Inpatient psychiatric services require active treatment documented in the patient’s hospital records.
- Meets these requirements:
- Is a qualified, licensed physician with admitting privileges at the hospital as permitted by state law. The physician can’t delegate the decision (order) to another person who isn’t state-authorized to admit patients or to whom the hospital’s medical staff hasn’t granted admitting privileges that apply to the patient.
- Is knowledgeable about the patient’s hospital course, medical plan of care, and current condition.
The admitting physician must complete and document the certification in the patient’s medical record before they’re discharged.
If a patient still needs active inpatient psychiatric treatment, follow this timeline for recertification:
- First recertification: By the 12th day of the hospital stay
- All other required recertifications: At least every 30 days, but a utilization review committee can create different review intervals on a case-by-case basis (for example, every third day)
Recertification must include:
- Documentation that inpatient treatment was and is still needed since the last certification or recertification for:
- Treatment you reasonably expect to improve the patient’s condition
- Diagnostic study
- Proof the patient still needs daily active treatment directly from, or under supervision of, IPF personnel
- Hospital records showing the services are:
- Intensive treatment services
- Admission or related services necessary for diagnostic study
- Equivalent services
One of these people must sign certification and recertification statements:
- The attending physician responsible for the case
- Another physician with case knowledge who’s authorized by the attending physician to sign
- A member of the hospital’s medical staff with case knowledge
Under the IPF PPS, IPFs get a predetermined federal per diem base rate for inpatient hospital services. The federal per diem base rate covers all IPF patient costs, including inpatient operating and capital-related costs (routine and ancillary services). It doesn’t include pass-through costs, like bad debts and graduate medical education.
The federal per diem base rate consists of a labor portion (LP)—which we adjust by the labor-related share (LRS)—and non-labor portion (NLP).
We calculate the IPF PPS per diem payment after adjusting the IPF PPS per diem base rate for facility and patient characteristics.
The IPF must provide all necessary Medicare-covered services directly or under arrangement. The IPF PPS payment is full payment for Medicare-covered inpatient operating and capital-related costs and Medicare-covered services provided in an IPF, and the deductible applies. The payment doesn’t cover the costs of an approved medical education program’s hospital services in an IPF.
Inpatient hospital services don’t include physician services or services provided by:
- Physician assistants
- Nurse practitioners
- Clinical nurse specialists
- Certified nurse-midwives
- Qualified psychologists
- Certified registered nurse anesthetists
We pay for these covered professional services separately under Medicare Part B.
When submitting claims, reasonably and consistently record the items and services patients got during an IPF stay. Even though IPFs get a per diem payment, you must completely and accurately report claim charges. This information helps us calculate payments and periodically refine the IPF PPS.
Facility-Level Adjustments
- We adjust the LP of the federal per diem base rate to account for geographic differences with an appropriate IPF wage index
- We apply an 18% payment adjustment for IPFs in rural locations, and IPFs where delineations changed from rural to urban in FY 2025 get a 3-year budget-neutral phaseout of their FY 2025 rural adjustment to reduce this financial impact
- We apply a 54% payment adjustment for the first day’s stay at IPFs with a qualifying emergency department (ED); we apply a 28% payment adjustment for the first day’s stay at IPFs without a qualifying ED
- We pay IPFs that train interns and residents a facility-level adjustment to the federal per diem rate
- For IPFs in Alaska and Hawaii, we adjust the federal per diem base rate NLP by a cost-of-living adjustment (COLA) factor
Patient-Level Adjustments
- Medicare Severity Diagnosis-Related Group (MS-DRG) adjustment, based on the patient’s principal psychiatric diagnosis
- Age
- Selected comorbidities, like renal failure, diabetes, and cardiac conditions
- Variable per diem adjustment
Additional Payments
IPFs get additional payments for:
- Each electroconvulsive therapy (ECT) treatment provided to a patient.
- Outlier cases, which are cases with extraordinarily high costs. An IPF is eligible for an outlier payment when its estimated total cost for a case exceeds a fixed dollar threshold (multiplied by the IPF’s facility-level adjustments for wage index, rural location, teaching status, and location in Alaska or Hawaii) plus the federal per diem payment amount for the case. For discharges occurring in cost reporting periods starting on or after October 1, 2027, we’ll limit an IPF’s total outlier payments to no more than 20% of its total IPF PPS payments. When the case qualifies for an outlier payment adjustment, we pay:
- 80% of the difference between the total cost and the adjusted threshold amount for the first 9 days
- 60% of the difference for all days after day 9
- Interrupted stays (when patients are discharged from and readmitted to the same IPF), which are considered continuous for the purposes of applying the variable per diem adjustment and determining if the case qualifies for an outlier payment.
Note: FY 2027 Final IPF PPS Rates and Adjustment Factors Addendum A has the federal per diem base rate and other payment-related updates.
Calculating IPF Prospective Payment
The IPF base payment rate per day in an FY is adjusted for differences in labor costs by the following:
Step 1. Geographic Wage & COLA Adjustment: Multiply the base rate by the LRS to get the LP. Multiply the LP of the base payment amount by the area wage index value to get the wage-adjusted labor share. Subtract the LP from the base rate to get the NLP. Multiply the NLP by the COLA, if applicable, to get the adjusted non-labor share. Add the wage-adjusted labor share to the adjusted non-labor share. The applicable federal per diem base rate is either the:
- Full federal per diem base rate
- Reduced federal IPF per diem base rate for IPFs that don’t report quality data
Step 2. Facility & Patient Adjustment Factor: Calculate the total facility- and patient-level adjustment factors, except the variable per diem and ED adjustments.

Note: Addendum A lists the FY 2027 teaching adjustment and rural adjustment factors.
Step 3. Partial Payment: Multiply Step 2’s adjustment factor by Step 1’s wage- and COLA-adjusted base rate to get a partially adjusted federal per diem base rate, without variable per diem and ED adjustments.
Step 4. Day by Day Variable Per Diem Adjustment: Multiply the partially adjusted federal per diem base rate for each day of the stay by its applicable variable per diem adjustment factor. For day 1, the factor is 1.54 if the IPF has a qualifying ED or 1.28 if the IPF has no qualifying ED.
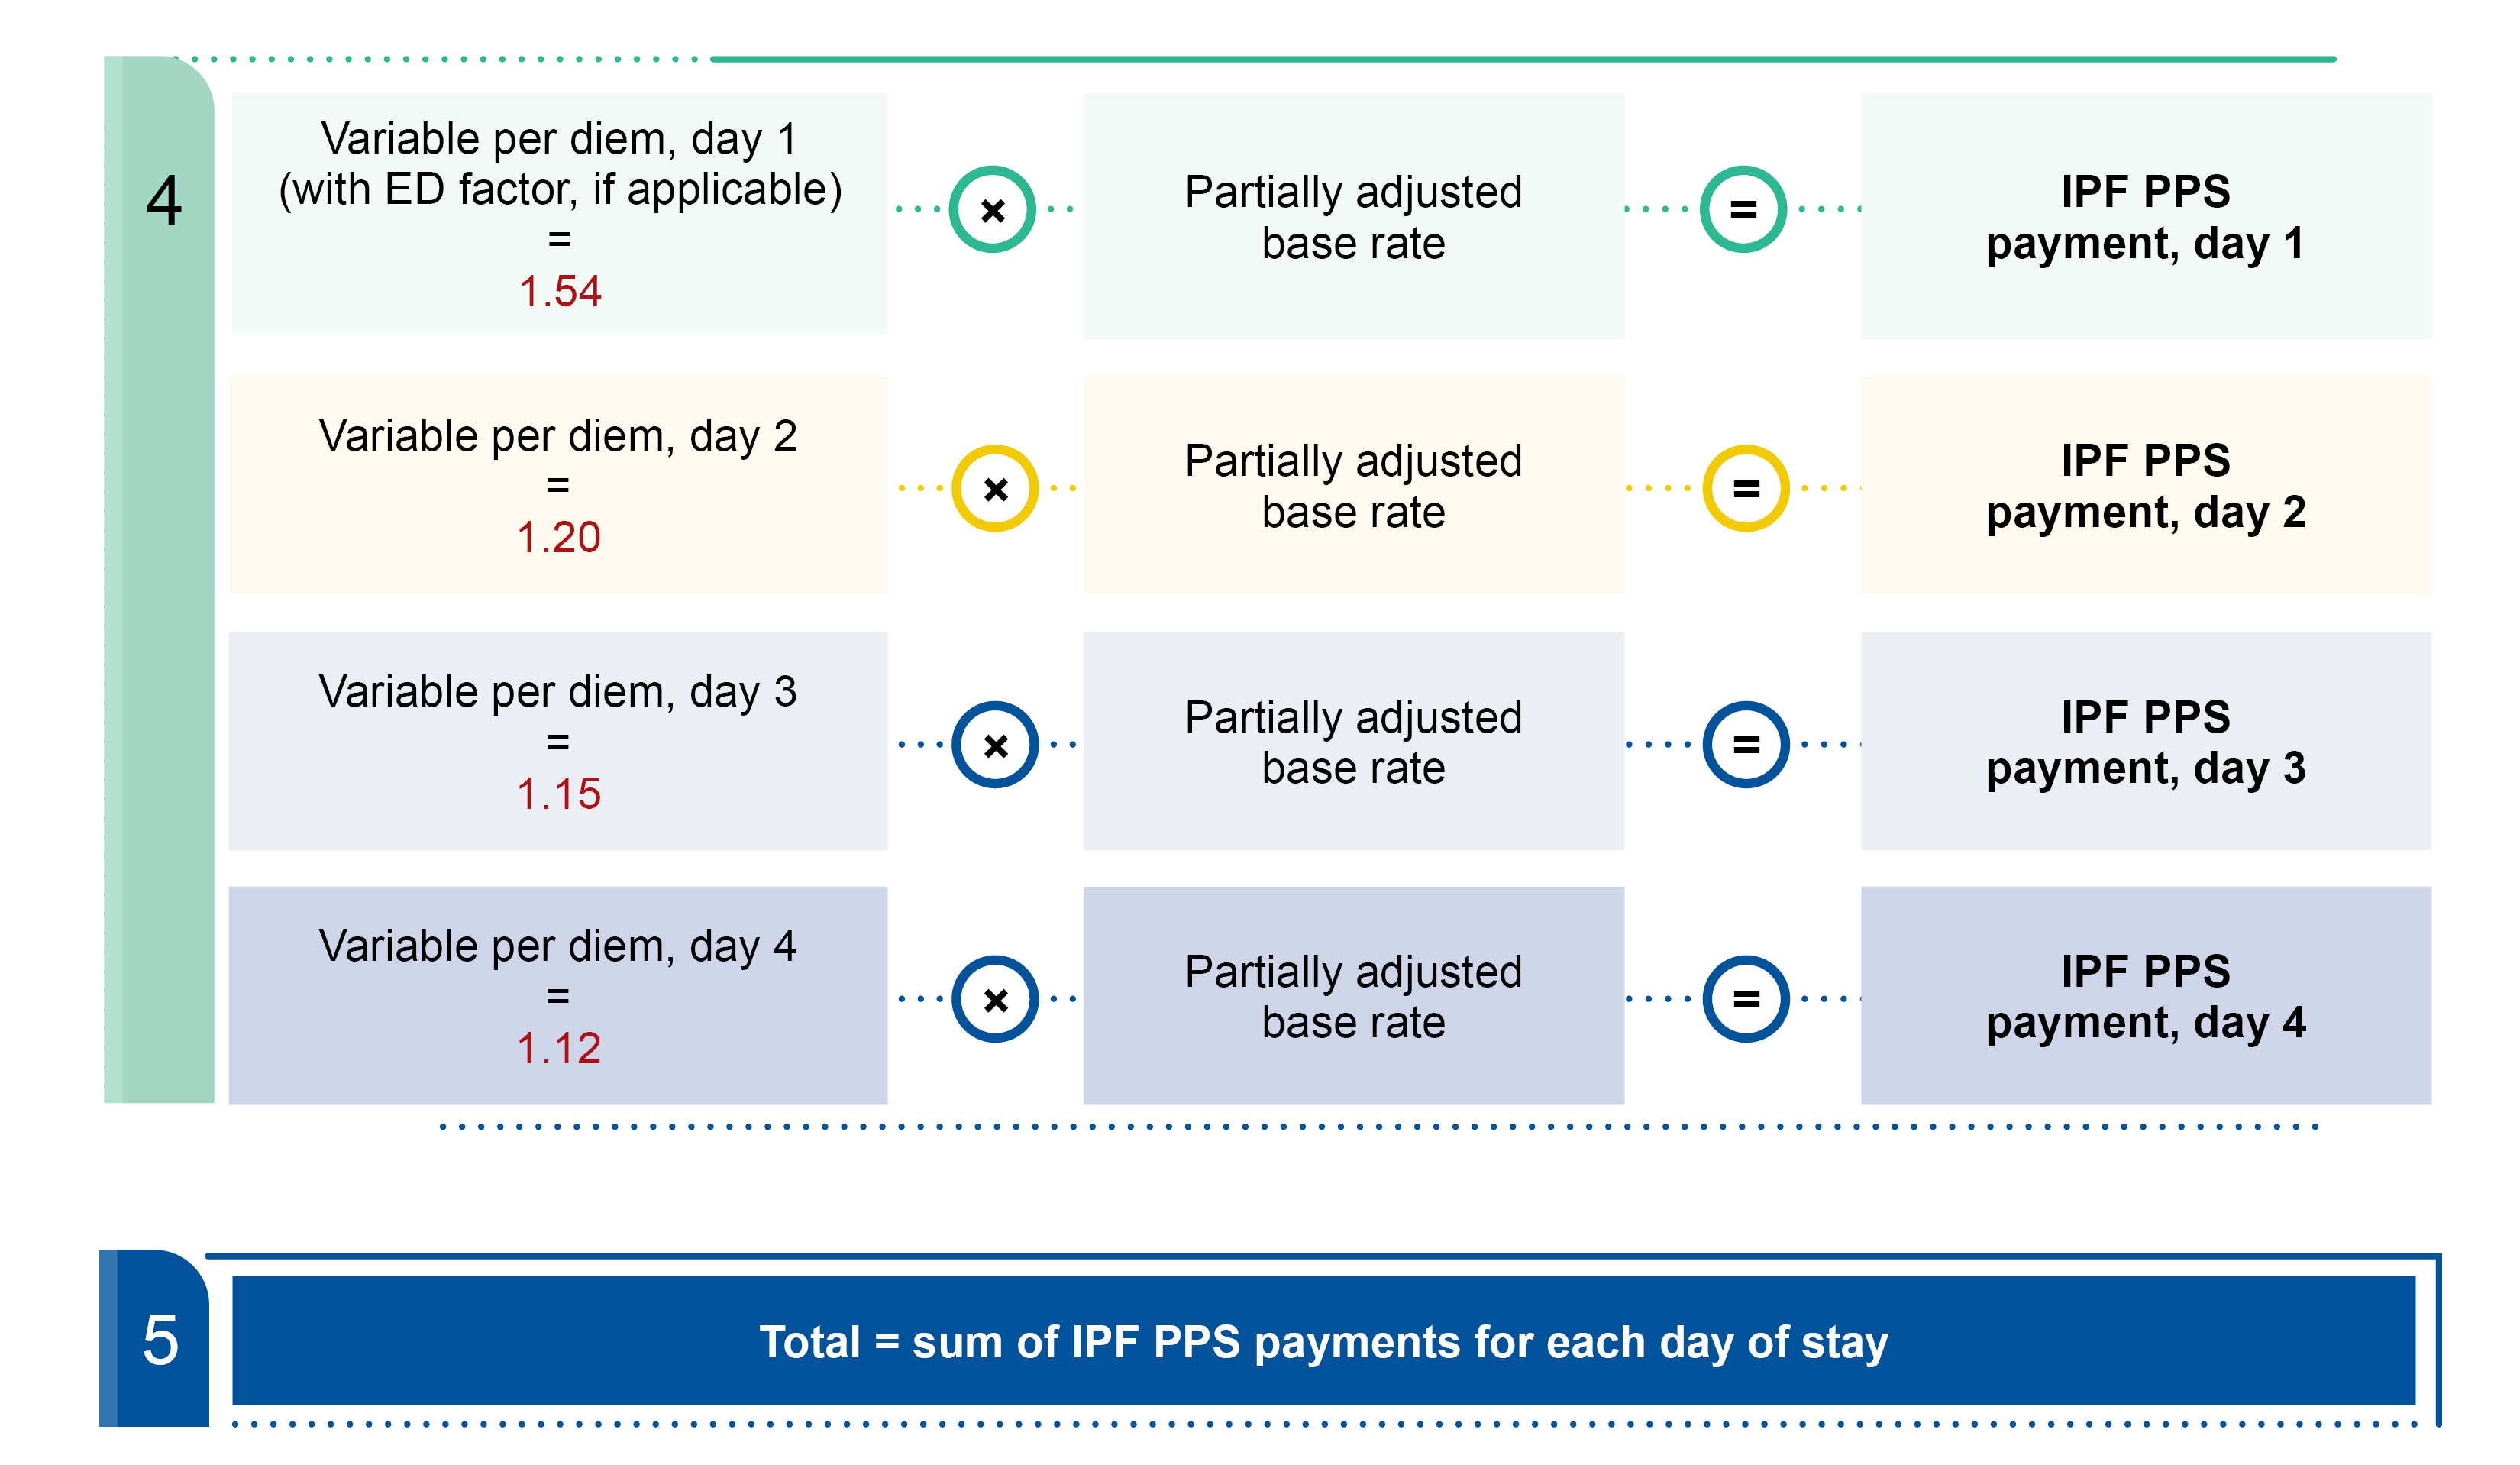
Step 5. Total IPF PPS Payments: Add the IPF PPS payments for each day of the stay to get the total IPF PPS payment amount.
Calculating ECT Treatment Payment
Multiply ECT treatment units provided during the stay by the appropriate wage- and COLA-adjusted ECT per treatment amount to get the total ECT payment. The appropriate ECT per treatment amount is either the:
- Full ECT per treatment amount
- Reduced ECT per treatment amount for IPFs that don’t report quality data
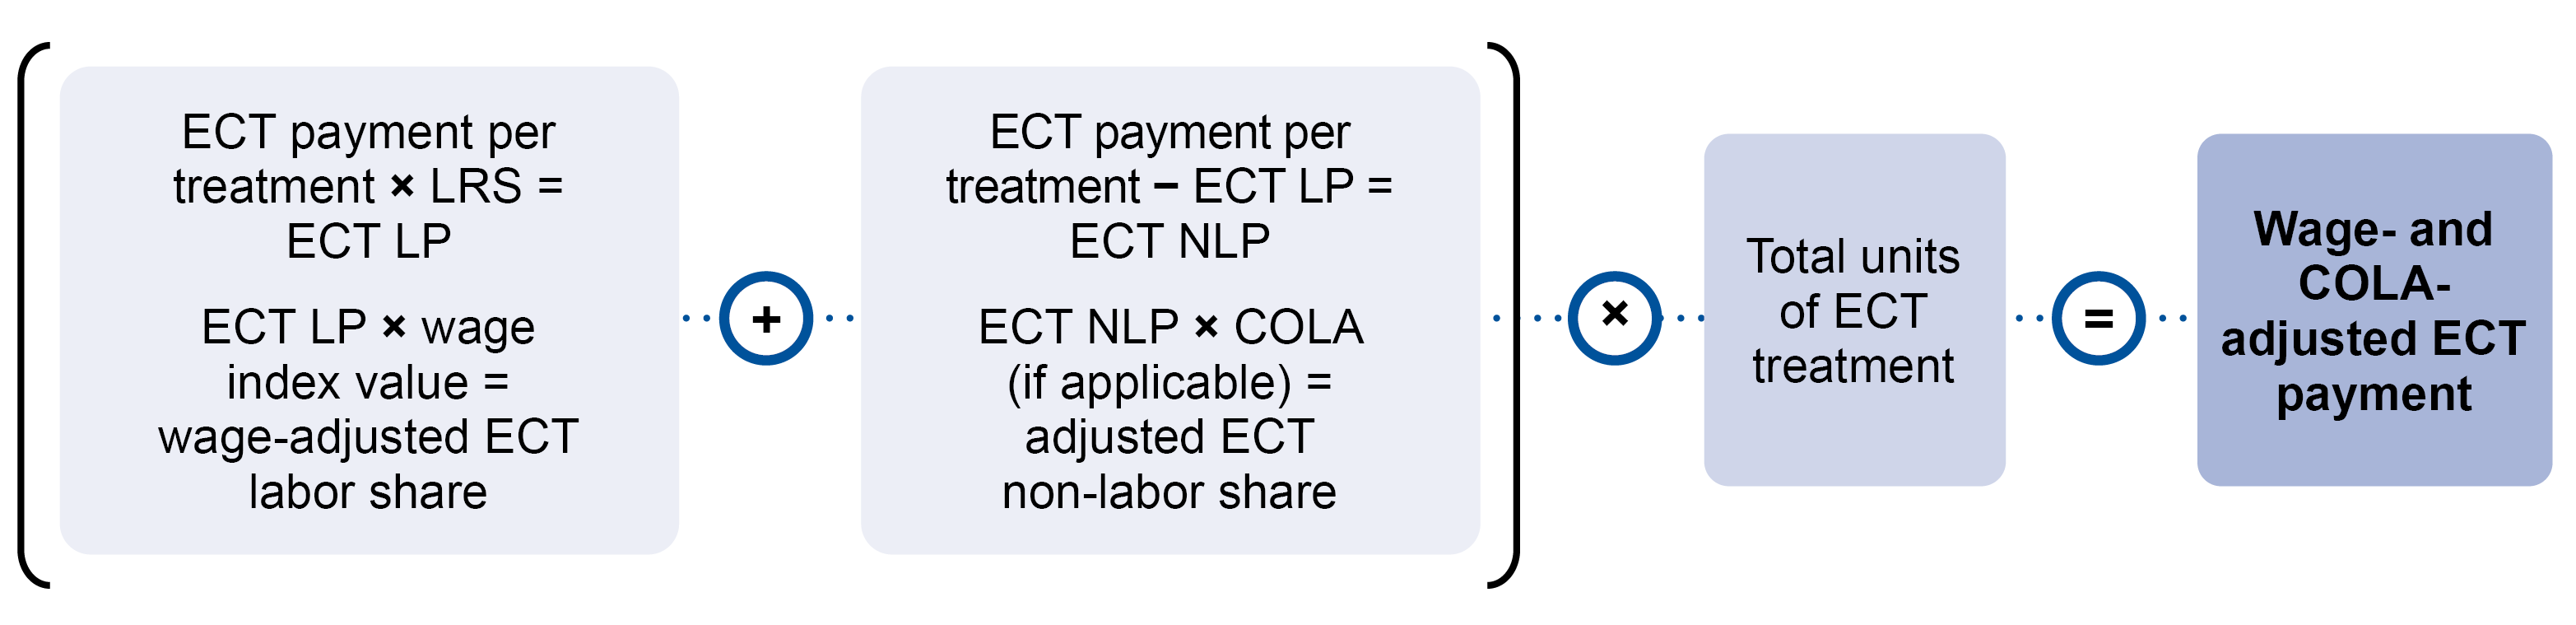
Calculating Outlier Payment
Starting October 1, 2027, we’ll use this methodology to calculate and apply a 20% facility-level cap for outlier payments:
Step 1. Determine if there were 50 or more IPF PPS stays during the cost reporting period. We exempt facilities with fewer than 50 stays during the cost reporting year from this policy.
Step 2. Calculate each facility’s total IPF PPS non-outlier payments for all discharges occurring during the cost reporting year.
Step 3. Divide the facility’s total non-outlier payments by 80% (0.8) to determine the maximum allowable total IPF PPS payment amount.
Step 4. Subtract the provider’s maximum allowable total IPF PPS payment from its actual total IPF PPS payment amount. If the result is greater than 0, then the facility’s total outlier payments exceed 20% of its total IPF PPS payments.
Step 5. If the facility’s total outlier payments exceed the 20% cap, reduce the outlier payment by the result of the calculation in Step 4.
The FY 2027 IPF productivity-adjusted market basket increase factor is 2.3%, which is a 3.2% market basket update reduced by a 0.9 percentage point productivity adjustment.
IPF PPS Regulations and Notices has the current and previous proposed and final rules for the IPF PPS.
Cost Report Data
Cost report data from Medicare freestanding and hospital-based IPFs helps calculate the major market basket stand-alone IPF cost weights. We calculate:
- Average freestanding IPF length of stay (LOS) from data reported on Worksheet S-3, Part I, Line 14
- Average hospital-based IPF LOS from data reported on Worksheet S-3, Part I, Line 16
Provider Reimbursement Manual – Part 2, Chapter 40 explains these worksheets.
Market Basket Updates
- The FY 2027 LRS is 78.9%.
- We continue to base the IPF wage index on the concurrent pre-floor, pre-reclassified Inpatient Prospective Payment System (IPPS) hospital wage index. We determine IPF labor market areas based on the core-based statistical area established by the Office of Management and Budget.
- We apply, in a budget-neutral manner, a permanent 5% cap on any decrease to a provider’s wage index from its wage index in the previous year.
Cost-to-Charge Ratios
National median cost-to-charge ratios (CCRs) apply to these IPFs:
- New IPFs that haven’t submitted their first Medicare cost report
- IPFs with an overall operating or capital CCR that exceeds 3 standard deviations above the corresponding national urban or rural average (the ceiling)
- Other IPFs that give the Medicare Administrative Contractor inaccurate or incomplete data for calculating a CCR
The IPF Quality Reporting (IPFQR) Program provides quality-of-care information so patients can make informed decisions about their health care options. It also encourages hospitals and providers to improve their quality of inpatient care by making sure they’re aware of, and reporting on, best practices for their facilities.
Quality Net and IPFQR Program Measures have the current quality reporting measures.
To meet the IPFQR Program requirements, IPFs must submit all quality measures. Eligible IPFs that don’t participate in the IPFQR Program in an FY or don’t meet all reporting requirements get a 2% annual market basket update reduction.
Starting October 1, 2027, IPFs may voluntarily submit an IPF-Patient Assessment Instrument (PAI) for all patients aged 18 and older, regardless of payer. Starting July 1, 2028, we’ll require IPFs that participate in the IPFQR Program to submit the IPF-PAI. Administer assessment items at admission and discharge, except where specified. To satisfy the IPFQR Program data reporting requirements, you’ll need to complete 100% of the IPF-PAI assessment items on at least 50% of your submitted IPF-PAIs for the initial mandatory reporting period of Q3 and Q4 CY 2028.
IPFs that don’t meet this threshold will get a 2% reduction to their annual payment update.
Resources
Inpatient Rehabilitation Facility Prospective Payment System
What’s Changed?
- Updated the FY 2027 market basket increase
- Clarified the 36-hour treatment requirement
- Updated the timeframe for holding the first interdisciplinary team meeting
Substantive content changes are in dark red.
Medicare pays inpatient rehabilitation hospitals and inpatient rehabilitation units, known collectively as inpatient rehabilitation facilities (IRFs), on a per-discharge prospective payment system (PPS).
We use the IRF-Patient Assessment Instrument (IRF-PAI) to classify Medicare patients into clinical, demographic, and payment groups that reflect their expected resource needs. We also use IRF-PAI information to monitor quality of care.
IRFs must complete the appropriate IRF-PAI sections when admitting and discharging each Medicare Fee-for-Service (FFS) and Medicare Advantage (MA) patient.
Under the IRF PPS, IRFs get a predetermined payment for goods and services they provide during each patient’s IRF stay. Federal rates reflect all IRF patient care costs, including routine, ancillary, and capital costs. Federal rates don’t include:
- Costs associated with operating approved educational activities as described in 42 CFR 413.75(a)(1) and 42 CFR 413.85(c)
- Bad debts
- Hemophilia blood product costs
To determine the federal payment amount for each IRF patient, we group patients by clinical condition and expected resource use.
- First, providers report an impairment group code in the IRF-PAI.
- Next, the data entry software assigns a rehabilitation impairment category according to the primary IRF admitting condition.
- Then, the software assigns a case-mix group (CMG) according to the patient’s functional status (motor and cognitive scores) and age. An unweighted motor score determines a patient’s CMG placement. The 18 items scored have an equal weight of 1. Within each CMG, we:
- Categorize cases into 1 of 4 tiers based on the patient’s comorbidities (conditions secondary to the principal admitting diagnosis)
- Make 1 tier payment for the case based on the patient’s highest-paying tier comorbidity
We adjust for:
- Interrupted stays
- Short stays less than 3 days
- Short-stay transfers (transfers to another institutional setting with an IRF length of stay less than the average CMG length of stay)
- Deaths
- High-cost outlier cases
We apply a permanent 5% cap in a budget-neutral manner on any decrease to a provider’s wage index from their previous year’s wage index.
Facility Characteristics
We adjust the hospital wage index to reflect geographic wage rate differences.
We apply an adjustment to the base rate for IRFs that treat a higher proportion of low-income patients.
IRFs with residency training programs get higher payment rates based on the number of interns and residents trained compared with their average daily census. We cap this adjustment.
We annually update rates to reflect:
- Inflation costs for IRF goods and services using a market basket index calculated for freestanding and hospital-based IRFs
- Changes in local wage rates
The FY 2027 IRF market basket increase factor is 2.3%, which is a 3.2% market basket update reduced by a 0.9 percentage point productivity adjustment.
Compliance Threshold
A facility must meet IRF classification requirements to get IRF PPS payment. At least 60% of the facility’s total inpatient population must need intensive IRF treatment for 1 or more of 13 medical conditions. We include comorbidities in the compliance threshold if they meet certain criteria.
Medicare Administrative Contractor Compliance Percentage
An IRF’s compliance percentage is the percentage of the total inpatient population requiring intensive IRF treatment for 1 or more of 13 medical conditions. Medicare Administrative Contractors (MACs) use compliance review period data to calculate the compliance percentage.
Except in the case of new IRFs, each compliance review period is 1 continuous 12-month period, starting 4 months before a cost reporting period and ending 4 months before the next cost reporting period.
MACs calculate the compliance percentage using:
- Presumptive Methodology: MACs use CMS software to analyze IRF PPS impairment group codes and etiologic diagnosis and comorbidity codes. IRFs send these ICD-10 Clinical Modification (CM) codes on the IRF-PAIs to us through iQIES.
- If at least 60% of the IRF’s inpatient population requires IRF treatment for 1 or more of the 13 medical conditions, then the IRF meets the 60% rule
- If the IRF doesn’t meet the 60% rule requirement based on the first part of the process, MACs must review cases from the IRF Arthritis Verification Report to make sure they meet regulatory requirements for inclusion in the IRF’s presumptive methodology compliance percentage, as explained in the Medicare Claims Processing Manual, Chapter 3, section 140.1.3
- Medical Records Review: MACs analyze a random medical records sample representing IRF inpatients during the compliance review period.
If at least 50% of your inpatient population is Medicare FFS or MA patients, then your MAC may use the presumptive methodology to determine if you meet the 60% compliance threshold. Your MAC may also review a random medical records sample if it believes that’s a more accurate way of calculating your compliance percentage. A MAC-calculated, random medical record sample always replaces the presumptive compliance percentage review.
MACs must use the random medical record sample method to calculate the compliance percentage when the facility meets both conditions:
- Its presumptive compliance percentage is less than the required 60% compliance threshold
- Its Medicare population (Medicare FFS plus MA patients) is less than half its total patient population
MACs must send results to the appropriate CMS Survey & Operations Group (CMS Location), which determines an IRF’s classification for the next cost reporting period. The classification status is effective for the entire cost reporting period.
If the CMS Location doesn’t classify a Medicare provider as an IRF, the provider isn’t eligible for payment under the IRF PPS. We pay them under the Inpatient PPS.
New IRF Units
We allow a hospital to open a new IRF unit anytime within the cost reporting year if the hospital notifies the Office of Program Operations & Local Engagement and their MAC in writing of the change at least 30 days before opening the new unit. In this circumstance, this change remains in effect for the rest of the cost reporting year.
When determining if an IRF admission is reasonable and necessary, MACs must consider these items in a patient’s IRF medical record:
- Preadmission screening
- Individual overall plan of care completed within 4 days of IRF admission
- Physician admission order
- Patient’s in-house IRF-PAI forms
- Medical necessity criteria
Submit IRF-PAI admission and discharge assessments together after a patient’s discharge. We won’t accept and process a Medicare Part A FFS IRF payment claim until we get and accept a corresponding IRF-PAI.
Medical Necessity Criteria
For Medicare to pay an IRF claim, the patient’s IRF stay must be reasonable and necessary according to 42 CFR 412.622(a)(3), (4), and (5) and the Medicare Benefit Policy Manual, Chapter 1, section 110.
We require a medical history and physical exam under the conditions of participation.
To meet medical necessity requirements, the patient must:
- Need active and ongoing therapeutic intervention in multiple therapy disciplines (physical therapy, occupational therapy, speech-language pathology, or prosthetics or orthotics therapy), 1 of which must be physical or occupational therapy.
- Start all the required therapy treatments and therapy evaluations within 36 hours from midnight on the day of admission.
- Generally need and get at least 3 hours of therapy per day at least 5 days per week and show measurable improvement in functional capacity or adapting to impairments. In certain well-documented cases, this intensive rehabilitation therapy program might instead be at least 15 hours per week within a period of 7 consecutive calendar days, starting with the IRF admission date.
- Be stable enough to actively participate in and benefit from intensive rehabilitation therapy at the time of IRF admission. Patients who are still completing treatment at the referring hospital should stay there until they can participate.
- Require supervision by a rehabilitation physician, defined as a licensed physician that the IRF determines has specialized training and experience in inpatient rehabilitation.
The rehabilitation physician must:
- Document that they reviewed and agree with the findings and results of the preadmission screening before the IRF admission.
- Document an individualized plan of care by day 4, where day 1 is the day of admission.
- Have at least 3 face-to-face meetings with the patient to assess their medical and functional status within the first week of admission. Starting the second week after admission, a non-physician practitioner with specialized training and experience in inpatient rehabilitation may conduct 1 of the 3 required face-to-face visits per week.
Preadmission Screening
The preadmission patient screening serves as the basis for the initial determination of whether the patient meets the requirements for IRF admission to be considered reasonable and necessary. A licensed or certified clinician must complete a preadmission patient screening for the patient within the 48 hours before IRF admission. This detailed, comprehensive evaluation of each patient’s condition and their need for medical treatment and rehabilitation therapy includes:
- Prior level of function
- Expected improvement level and time expected to reach it
- Clinical complications risk
- Conditions requiring rehabilitation
- Required treatments (physical therapy, occupational therapy, speech-language pathology, prosthetics, or orthotics); 1 of the therapies must be physical therapy or occupational therapy
- Anticipated discharge destination
We can accept a preadmission screening completed more than 48 hours before IRF admission if the IRF assesses the patient’s updated medical and functional status—by phone or in person—and documents it in the patient’s medical record in the 48 hours immediately before admission.
We deny the claim if the rehabilitation physician doesn’t document that they reviewed and agreed with the preadmission screening findings before the IRF admission.
Interdisciplinary Team Meetings
The first interdisciplinary team meeting must occur on or before day 4 of the patient’s admission, with the day of admission being day 1. This aligns the first interdisciplinary team meeting with the plan of care development. Also, hold subsequent interdisciplinary team meetings within 7 days of the prior interdisciplinary team meeting throughout the IRF stay.
A rehabilitation physician may lead the weekly interdisciplinary team meetings in person, by video, or by phone. All team members must have current knowledge of the patient’s medical and functional status.
Team meetings must involve a:
- Rehabilitation physician
- Registered nurse with rehabilitation training or experience
- Social worker or case manager (or both)
- Licensed or certified therapist from each therapy discipline involved in the patient’s care
Keep the meetings’ results and findings, along with the rehabilitation physician’s agreement with those results and findings, in the patient’s medical record.
Interdisciplinary team meetings’ documentation should include participant names and professional titles. You don’t need signatures from interdisciplinary team meeting participants other than from the rehabilitation physician, whose signature indicates their agreement.
The IRF Quality Reporting Program (QRP) provides quality-of-care information so patients can make informed decisions about their health care options. It also encourages hospitals and providers to improve their quality of inpatient care by making sure they’re aware of, and reporting on, best practices for their facilities.
IRF QRP FAQs has more information.
To meet the IRF QRP requirements, IRFs must submit all quality measures. Eligible IRFs that don’t participate in the IRF QRP in an FY or don’t meet all reporting requirements get a 2% annual increase factor reduction.
IRFs may qualify for a reconsideration and an exception or extension.
Starting with the FY 2026 IRF QRP, we expanded the IRF quality data reporting requirements, which applied to all IRF patients with Part A FFS and MA plans, so that IRFs started collecting data on all IRF patients, regardless of payer. This policy ensures that:
- All IRF patients get the same quality of care
- All provider metrics reflect performance across the IRF patient network
Providers must collect the IRF-PAI assessment on all patients getting IRF care, regardless of payer.
Resources
Long-Term Care Hospital Prospective Payment System
What’s Changed?
We updated the FY 2027 market basket increase factor.
Substantive content changes are in dark red.
Long-term care hospitals (LTCHs) generally treat medically complex patients who need longer hospital stays than they could get at short-term acute care hospitals. LTCHs must meet the same Medicare certification requirements as short-term acute care hospitals. For Medicare payment classification purposes, an LTCH must have an average inpatient length of stay (LOS) greater than 25 days.
CMS makes annual updates to the LTCH payment rates based on the market basket index. Per federal regulations, we then reduce the rates through a productivity adjustment.
The FY 2027 LTCH Prospective Payment System (PPS) market basket increase factor is 2.3%, which is a 3.2% market basket update reduced by a productivity adjustment of 0.9 percentage points.
For LTCHs that don’t report quality data, we further reduce the market basket rate by 2 percentage points.
We pay LTCHs under the LTCH PPS. Under this payment system, we set base payment rates for inpatient stays based on several factors, including:
- Patient’s diagnosis
- Services or treatment provided
- Illness severity
A hospital gets a single payment for each case, depending on the payment classification assigned at discharge. The classification systems are:
- Inpatient Prospective Payment System (IPPS): Medicare Severity Diagnosis-Related Groups (MS-DRGs)
- LTCH PPS: Medicare Severity Long-Term Care Diagnosis-Related Groups (MS-LTC-DRGs)
We group each patient stay using:
- One principal diagnosis
- Up to 24 secondary diagnoses
- Up to 25 procedure codes
- Age
- Sex
- Patient discharge status
We use the latest available discharge data from LTCHs to make annual updates to each MS-LTC-DRG and its predetermined average length of stay (ALOS). We pay LTCHs for each discharge based on the MS-LTC-DRG if the discharge meets exclusion requirements from the site neutral payment rate. We pay for cases assigned to an MS-LTC-DRG based on the federal payment rate, including payment and policy adjustments.
When a patient doesn’t meet specific criteria, we pay for LTCH discharges at a site neutral payment rate, which is generally the lower of these:
- IPPS comparable per diem amount (calculated under the short-stay outlier (SSO) policy, including the applicable high-cost outlier (HCO) payment)
- Estimated case costs calculated by multiplying allowable charges by the LTCH’s cost-to-charge ratio (CCR)
Note: The Bipartisan Budget Act of 2018 specified that the IPPS comparable amount shall be reduced by 4.6% for FYs 2018 through 2026.
We exclude discharges from the site neutral payment rate and pay based on the standard federal payment rate if both of these apply:
- The discharge from the LTCH doesn’t have a principal diagnosis relating to a psychiatric diagnosis or to rehabilitation based on the assigned MS-LTC-DRG
- The provider directly admits the patient from an IPPS hospital and the patient had either:
- At least 3 days in an intensive care or coronary care unit at the IPPS hospital
- At least 96 hours of respiratory ventilation services at the LTCH
SSO, HCO, fixed-loss amount, and interrupted stay payment policy adjustments all apply to site neutral and standard federal payment rate discharges except where noted.
Short-Stay Outlier
The SSO policy helps prevent inappropriately paying for cases without a full episode of care. SSO payment adjustments apply only to the standard federal payment rate discharges and may happen when a patient:
- Experiences an acute condition that needs urgent treatment or more intensive rehabilitation and the LTCH discharges them to another facility
- Doesn’t need an LTCH care level and the LTCH discharges them to another facility
- Is discharged to their home
- Dies within the first several days after LTCH admission
- Exhausts LTCH benefits during the stay
We adjust the MS-LTC-DRG payment for SSOs when the LOS ranges from 1 day up to and including 5/6 of the ALOS for the case’s assigned MS-LTC-DRG.
We don’t apply an adjustment when the LOS is more than 5/6 of the ALOS for the case’s assigned MS-LTC-DRG. In this situation, the LTCH gets the full MS-LTC-DRG payment.
Note: When calculating the SSO adjustment, we cap the SSO threshold (5/6 of the ALOS for the MS-LTC-DRG) at 25 days. We never subject stays of 25 days or more to the SSO policy.
This policy doesn’t apply to site neutral discharges.
We blend the MS-LTC-DRG per diem amount with what we would pay under the IPPS, calculated as a per diem amount and capped at the full IPPS comparable amount.
SSO Payments When a Patient Exhausts Benefits During an LTCH Stay
We base LTCH payments on the patient’s covered benefit days until the LOS triggers a full MS-LTC-DRG payment. This means a patient’s remaining benefit days and length of hospital stay affect LTCH payments and may result in an SSO payment adjustment.
| If | Then | Example |
|---|---|---|
| The patient uses regular episode benefit days during an LOS below the SSO MS-LTC-DRG threshold |
|
The MS-LTC-DRG SSO threshold is 25 days, and the patient’s benefit days end on day 15. The patient’s LOS is 20 days.
|
| If | Then | Example |
|---|---|---|
| The patient uses all benefit days for an episode during an LOS exceeding the SSO MS-LTC-DRG threshold |
|
The MS-LTC-DRG SSO threshold is 25 days, and the patient’s benefit days end on day 30. The patient’s LOS is 35 days.
Note: The patient wouldn’t pay until the first day the stay qualifies as an HCO (refer to the High-Cost Outlier section for more information). |
Note: We cover 90 benefit days for an episode of care under the inpatient hospital benefit. Each patient has 60 lifetime reserve days, which the patient may use for non-covered days of an episode of care that exceeds 90 days.
High-Cost Outlier
The HCO policy adjusts the applicable LTCH PPS payment rate (site neutral rate or standard federal rate) for LTCH stays with costs exceeding what’s typical for similar cases. To qualify for an HCO payment, an LTCH’s estimated treatment costs must exceed the outlier threshold. We calculate the applicable outlier threshold as the case’s applicable LTCH PPS payment plus the applicable fixed-loss amount.
The HCO payment equals 80% of the difference between the estimated case cost and the outlier threshold.
For SSO cases, we calculate the outlier threshold by adding the applicable fixed-loss amount to the adjusted SSO MS-LTC-DRG payment. If the estimated SSO case cost exceeds the outlier threshold, it qualifies for an HCO payment.
We set 2 fixed-loss amounts:
- Site neutral payment rate
- Standard federal rate
The HCO adjustment:
- Improves the accuracy of LTCH PPS hospital- and patient-resource costs
- Cuts LTCH financial losses from treating patients who need costlier care
- Limits LTCH losses to the fixed-loss amount and cost percentages above the marginal cost factor
- Discourages LTCHs from underserving high-cost patients
Medicare Administrative Contractors (MACs) use Pricer software to determine if enough medically necessary benefit days are in the outlier period. If a patient has enough benefit days, the MAC processes the claim as usual, and the LTCH takes no other action. If a patient doesn’t have enough benefit days, the MAC returns the claim to the LTCH for correction, indicating the correct HCO threshold amount.
HCO Payments When a Patient Exhausts Benefits During an LTCH Stay
We make HCO payments for:
- Days the patient has Medicare coverage (regular, coinsurance, or lifetime reserve days) for the part of the stay beyond the HCO threshold
- Covered costs for medically necessary days when the patient has a benefit day available
| If | Then | Example |
|---|---|---|
|
The LTCH gets an HCO payment with an SSO-adjusted payment for covered medically necessary benefit days | The LTCH admits a standard federal rate patient with 5 remaining benefit days grouped to an MS-LTC-DRG with a 30-day ALOS.
|
| If | Then | Example |
|---|---|---|
|
The LTCH gets an HCO payment with the full LTCH PPS payment for covered medically necessary benefit days | The LTCH admits a standard federal rate patient with 36 remaining benefit days grouped to an MS-LTC-DRG with a 30-day ALOS.
|

“Full applicable LTCH PPS payment” means the standard federal rate (including the SSO adjustment) or the site neutral payment rate, depending on the LTCH case. “Applicable HCO threshold” means the HCO threshold based on the standard federal rate fixed-loss amount or site neutral fixed-loss amount, depending on the LTCH case.

| If | Then | Example |
|---|---|---|
|
|
The LTCH admits a standard federal rate patient with 36 remaining benefit days grouped to an MS-LTC-DRG with a 30-day ALOS.
|
If the patient’s benefits are exhausted during the LTCH stay, determine the:
- Day when the case cost reaches the applicable HCO threshold (use charges per day and the CCR)
- Number of benefit days the patient has left
To calculate the HCO, use only the costs for the available benefit days after the patient’s case cost reaches the HCO threshold. If the patient remains under care after exhausting their benefits, they pay the costs of those remaining days.
Any changes to HCO payments under the LTCH PPS outlier reconciliation policy don’t retroactively affect a patient’s lifetime reserve days or their coverage status, benefits, or payments under Medigap or Medicaid.
HCO Fixed-Loss Amounts
The fixed-loss amount for standard federal payment rate cases is the amount allowing yearly projected total HCO payments to equal 7.975% of the total LTCH PPS standard federal payment rate payments estimated for that year (full MS-LTC-DRG payments or adjusted SSO amount plus HCO payments).
We include estimated uncompensated care payments in the outlier fixed-loss cost threshold calculation. Specifically, in all cases, we use the estimated per-discharge uncompensated care payments for hospitals eligible for these payments.
The applicable HCO threshold for site neutral payment rate cases is the sum of the case’s site neutral payment rate and the IPPS fixed-loss amount. We set the site neutral case fixed-loss amount to equal the IPPS fixed-loss amount.
We estimate each case’s cost using the provider-specific file CCR. When that CCR isn’t available, we use the applicable statewide average CCR.
MACs estimate a case’s cost by multiplying the Medicare-covered charges by the LTCH’s overall CCR, which is based on the most recently settled or tentatively settled cost report.
These CCR revisions or determinations also apply:
- We may ask MACs to use an alternative CCR showing recent substantial increases or decreases in a hospital’s charges
- LTCHs may ask their MAC to use a higher or lower CCR based on substantial evidence when their CMS Regional Office approves it
- MACs assign annually the statewide average CCR to LTCHs with CCRs above the maximum ceiling
- MACs use an LTCH’s actual CCR rather than the statewide average LTCH CCR with CCRs below the minimum floor
- MACs may use the statewide average CCR when the LTCH CCR is undetermined (for example, before a new LTCH submits its first Medicare cost report or when data isn’t available to calculate the CCR because it’s missing or incorrect)
The LTCH PPS outlier policy allows for reconciling HCO payments at cost report settlement and accounts for differences between the estimated and actual CCR for the period when the discharge occurs.
Interrupted Stay
An interrupted stay happens when an LTCH discharges a patient to an acute care hospital, inpatient rehabilitation facility (IRF), skilled nursing facility (SNF), swing bed, or home and then the same LTCH readmits the patient for more medical treatment within a specified period. For example, an interrupted stay may occur when an LTCH discharges a patient for treatment for services which are unavailable in the LTCH.
The 2 types of interrupted stays are:
- 3 days or less
- Greater than 3 days
The interruption day count starts the day of discharge (the first day the patient is away from the LTCH at midnight).
3-Day or Less Interruption Example
If an LTCH discharges a patient on September 2, the 3-day or less interrupted stay policy determines payment if the LTCH readmits the patient to the same LTCH on September 2, 3, or 4.
If an LTCH discharges a patient and readmits them to the same LTCH within 3 days, the patient may:
- Get outpatient or inpatient tests, treatment, or care at an inpatient acute care hospital, IRF, SNF, or swing bed. Outpatient or inpatient care during interruption is part of a single LTCH care episode and bundled into the LTCH payment. If a patient gets tests or procedures during a 3-day interruption and the LTCH pays the provider under arrangements, the total patient day count includes all interrupted days.
- Have an intervening patient stay at home for up to 3 days with no tests, treatment, or care. If the patient doesn’t get care during the 3-day interruption, the LTCH can’t use days away in the total LOS. However, if, during an interruption, the patient gets care that the LTCH pays for under arrangements, the LTCH uses all interruption days in that patient’s LOS.
Greater Than 3-Day Interruption Example
If an LTCH discharges a patient on September 2, the greater than 3-day interrupted stay policy determines payment if the patient is readmitted to the same LTCH between September 5 and the applicable provider’s fixed-period threshold.
For a greater than 3-day interruption, the LTCH must:
- Discharge the patient
- Admit them directly to an inpatient acute care hospital, IRF, SNF, or swing bed
- Readmit them to the original LTCH within the applicable specified period in Table 8
| Discharge To | Interrupted Stay Fixed Period |
|---|---|
| Inpatient acute care hospital | Between 4 and 9 consecutive days |
| IRF | Between 4 and 27 consecutive days |
| SNF or swing bed | Between 4 and 45 consecutive days |
We treat an interrupted stay episode as 1 discharge for payment and make 1 LTCH PPS payment. Interrupted stays are eligible for HCO payments.
We pay separately for an intervening inpatient stay at the acute care hospital, IRF, SNF, or swing bed.
These examples don’t qualify as interrupted stays:
- The patient’s stay at an acute care inpatient hospital, IRF, SNF, or swing bed exceeds the fixed-day period
- The patient is discharged to a facility type other than an acute care inpatient hospital, IRF, SNF, or swing bed
- The patient is discharged to more than 1 facility or goes home between LTCH stays
If the stay disruption doesn’t meet the interrupted stay definition, the original discharge ends the patient’s first stay. If an LTCH readmits the patient, the second admission starts a new stay. The LTCH gets 2 LTCH PPS payments (full MS-DRG payment or adjusted SSO payment, as applicable) for 2 patient stays:
- Payment for the first stay
- Payment for the stay after an LTCH readmission
Interrupted Stay Billing Requirements
- Report the stay’s dates in Statement Covers Period:
- The from date is the original admission date
- The through date is the final discharge date
- Report payable days in the Covered Days field (value code 80)
- Report interrupted days in the Non-Covered Days field (value code 81)
- Report occurrence span code (OSC) 74 with the dates the patient was absent at midnight (for interruptions of more than 1 day):
- The OSC from date is the initial LTCH discharge date
- The OSC through date is the last LTCH date the patient wasn’t present at midnight
- Don’t change the principal diagnosis when the patient is readmitted to the LTCH; if the patient has other medical conditions when they return, report the diagnosis codes on the claim
- Use revenue code 018X to show the number of interruption days
Discharge Payment Percentage Adjustment
An LTCH’s discharge payment percentage is the ratio of the LTCH’s discharges that got the standard federal rate payment to its total Medicare discharges under the LTCH PPS. If an LTCH’s discharge payment percentage for a cost reporting period isn’t at least 50%, this payment adjustment policy applies after we calculate the percentage and notify the LTCH.
For cost reporting periods subject to this adjustment, the discharge payment percentage adjustment is an:
- Amount equivalent to the hospital IPPS payment
- Added payment for HCO cases that’s based on the IPPS hospital fixed-loss amount in effect at the time of the LTCH discharge
The payment adjustment ends when the calculated cost reporting period’s discharge payment percentage is at least 50%. We may subject the LTCH to this adjustment again if, after reinstatement, the discharge payment percentage falls below 50%.
LTCHs subject to a cost reporting period payment adjustment can get a special probationary reinstatement. They can do this by getting the payment adjustment delayed if, for at least 5 consecutive months of the 6 months before the cost reporting period, they have a discharge payment percentage of at least 50%.
For any cost reporting period where the payment adjustment would have applied without a delay, the payment adjustment will be applied for all discharges in the cost reporting period if the discharge payment percentage isn’t at least 50%.
The LTCH Quality Reporting Program (QRP) makes quality-of-care information available so patients can make informed decisions about their health care options. It also encourages hospitals and providers to improve their quality of inpatient care by making sure they’re aware of, and reporting on, best practices for their facilities and type of care.
LTCH QRP Measures Information has the current quality reporting measures. Find more information in the LTCH QRP FAQs.
Eligible LTCHs that don’t participate in the LTCH QRP in an FY or don’t meet all reporting requirements get a 2% reduction in their annual payment update.
LTCHs may qualify for a reconsideration and an exception and extension.
Resources
Skilled Nursing Facility Prospective Payment System
What’s Changed?
- Updated the market basket increase
- Updated Minimum Data Set (MDS) reporting requirements to include all payers, starting October 1, 2029
Substantive content changes are in dark red.
Medicare pays for skilled nursing facility (SNF) services per diem under a prospective payment system (PPS). Under section 1888(e)(4)(E) of the Social Security Act, the SNF PPS per diem payment covers all Medicare Part A SNF services (routine, ancillary, and capital-related costs), except approved educational activities and services excluded from SNF consolidated billing (CB) costs.
We determine SNF payments by adjusting base payment rates for geographic differences in labor costs and case-mix, and we calculate separate base rates for urban and rural areas.
Payment rates include an add-on to the Medicare Part B services cost estimate. We pay this add-on for SNF patients during a Part A-covered stay.
We base the standardized per diem rates on national data from urban and rural areas. Case-mix and wage adjustments apply to these per diem rates. We pay SNFs at the full federal rate.
We update federal rates annually to reflect changes in:
- Cost of goods and services SNFs purchase to provide care using the SNF market basket index. When we calculate the market basket index:
- We include a forecast error adjustment when the difference between forecast and actual changes in the market basket exceeds a 0.5% threshold for the most recently available final FY data.
- The FY 2027 SNF market basket update is 2.4%. The update reflects the 3.3% market basket increase, reduced by the 0.9 percentage-point productivity adjustment. We didn’t apply the 0.2% forecast error adjustment.
- Local wage rates using the latest hospital wage index.
- Facility performance in the SNF Value-Based Purchasing (VBP) Program.
Two federal rate adjustments reflect a SNF’s reimbursement.
- Geographic Differences in Wage Rates
We apply a permanent 5% cap on any decrease to a SNF’s wage index from its previous year’s wage index. This provision aims to provide stability and predictability in a SNF’s reimbursement by limiting sudden, significant drops in its wage index. The wage index makes payment adjustments based on geographic variations in labor costs.
A SNF’s wage index for FY 2027 wouldn’t be less than 95% of its final FY 2026 wage index regardless of whether the SNF is part of an updated core-based statistical area.
For subsequent years, a SNF’s wage index wouldn’t be less than 95% of its previous FY’s wage index.
We pay a new SNF the wage index for the area where it’s geographically located for its first full or partial FY with no cap applied, because a new SNF wouldn’t have had a wage index in the previous FY.
- Patient Case Mix
The patient case mix shows the number of resources typically needed for each patient’s clinical condition identified during the resident assessment process. It uses the Patient Driven Payment Model (PDPM) patient classification system to classify SNF patients.
PDPM classifies patients into 5 case-mix index (CMI)-adjusted components, and each component uses different measures.
| Component | Measure |
|---|---|
| Physical therapy (PT) | Clinical category, functional score |
| Occupational therapy (OT) | Clinical category, functional score |
| Speech-language pathology (SLP) | Presence of acute neurologic condition, SLP-related comorbidity, cognitive impairment, mechanically altered diet, or swallowing disorder |
| Non-therapy ancillary (NTA) | NTA comorbidity score |
| Nursing | Functional score |
Note: We apply a variable per diem (VPD) resource-use adjustment rate for PT, OT, and NTA payments.
To calculate each payment component, multiply the CMI linked to the patient’s case-mix group by the wage-adjusted component base rate and then by the VPD schedule-specific day, when applicable. Add each component payment to the non-case-mix component payment rate to create the patient’s PDPM per diem rate.
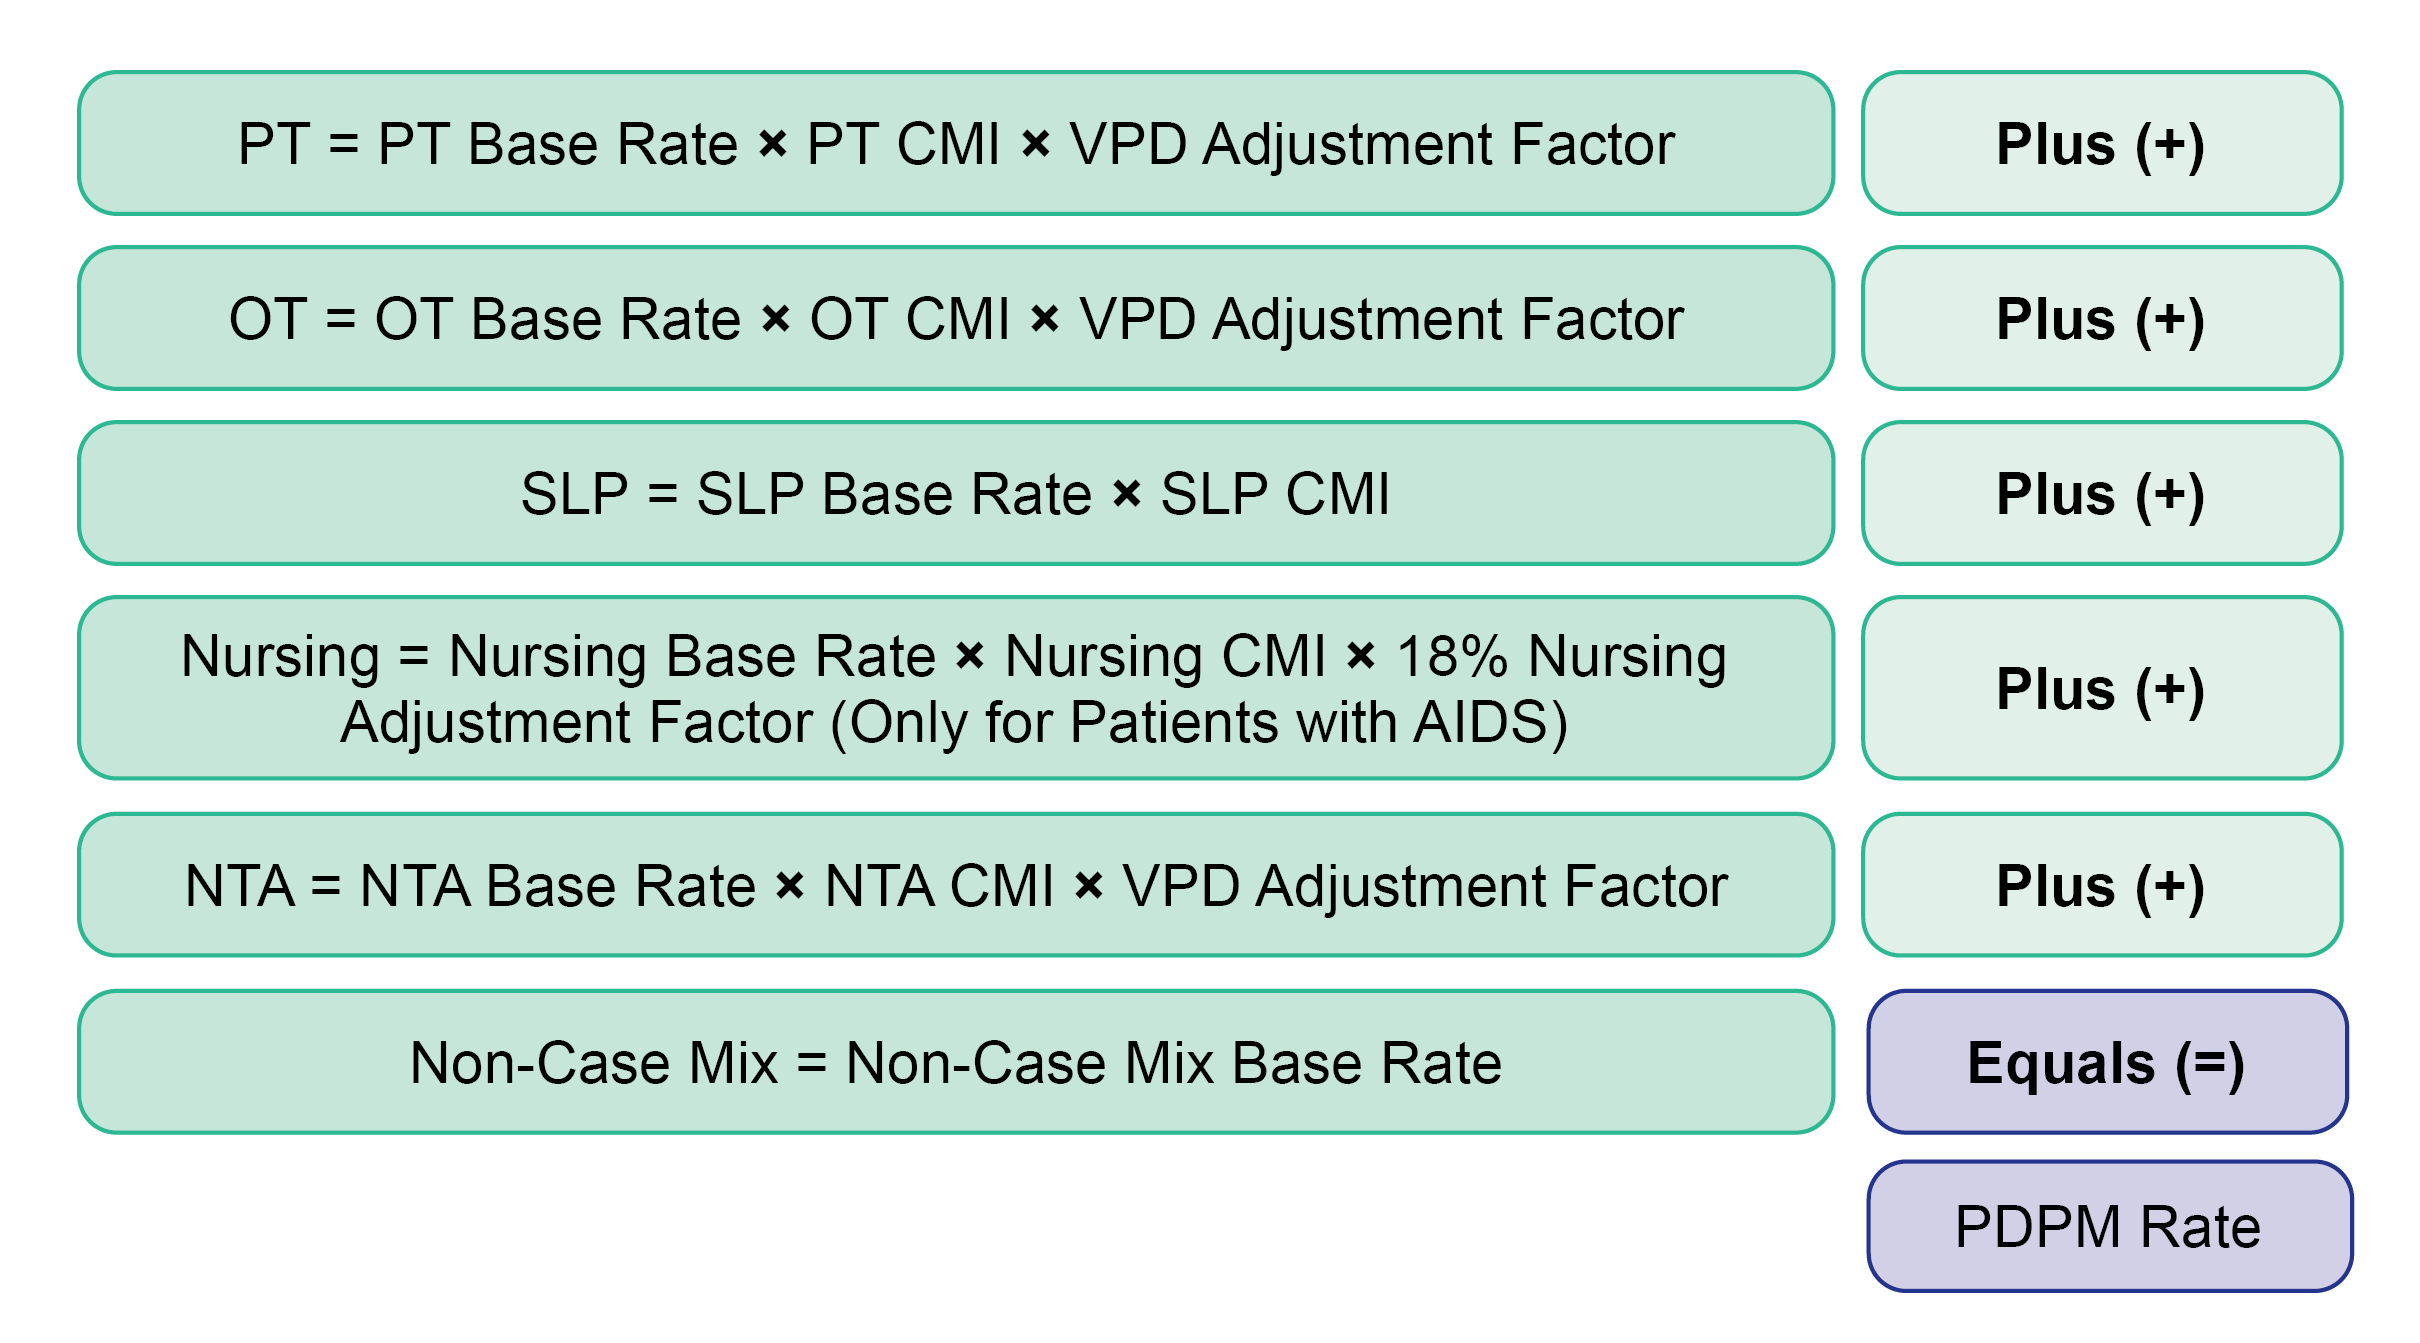
Clinical Category & Functional Status
PT and OT components use 2 classifications:
- Clinical category
- Functional status
Clinical Category
We base the clinical category on the primary SNF stay diagnosis code by mapping the ICD-10 Clinical Modification (CM) codes recorded on the Minimum Data Set (MDS) in Item I0020B to 1 of these PDPM primary diagnosis clinical categories:
- Acute Infections
- Acute Neurologic
- Cancer
- Cardiovascular and Coagulations
- Major Joint Replacement or Spinal Surgery
- Medical Management
- Non-Orthopedic Surgery
- Non-Surgical Orthopedic/Musculoskeletal
- Orthopedic Surgery (Except Major Joint Replacement or Spinal Surgery)
- Pulmonary
Some ICD-10-CM codes can map to a different clinical category from the default if the patient had a surgical procedure during the previous inpatient stay. Follow the instructions in the MDS Resident Assessment Instrument Manual and download the current FY PDPM ICD-10 Mapping file from the PDPM webpage.
Mapping the ICD-10-CM diagnosis or surgical category classifies a SNF resident into each of the clinical categories listed. Each year we consider stakeholder ICD-10-CM mapping suggestions.
PDPM PT & OT Clinical Categories
Given similar costs among certain PT and OT clinical categories, we grouped certain patient clinical classification categories together:
- Major Joint Replacement or Spinal Surgery
- Non-Orthopedic Surgery and Acute Neurologic
- Other Orthopedic
- Non-Surgical Orthopedic/Musculoskeletal
- Orthopedic Surgery (Except Major Joint Replacement or Spinal Surgery)
- Medical Management
- Acute Infections
- Cancer
- Cardiovascular and Coagulations
- Medical Management
- Pulmonary
Functional Status
We calculate the PDPM PT and OT functional score in Table 2 using MDS 3.0 data based on 10 Section GG items that proved highly predictive of PT and OT costs per day:
- 1 eating item
- 1 oral hygiene item
- 1 toileting item
- 2 bed mobility items
- 3 transfer items
- 2 walking items
| Section GG Item | Functional Score Range |
|---|---|
| GG0130A1—Self-care: Eating Admission Performance | 0–4 |
| GG0130B1—Self-care: Oral Hygiene Admission Performance | 0–4 |
| GG0130C1—Self-care: Toileting Hygiene Admission Performance | 0–4 |
| GG0170B1—Mobility: Sit to Lying Admission Performance | 0–4 (average of 2 items) |
| GG0170C1—Mobility: Lying to Sitting on Side of Bed Admission Performance | 0–4 (average of 2 items) |
| GG0170D1—Mobility: Sit to Stand Admission Performance | 0–4 (average of 3 items) |
| GG0170E1—Mobility: Chair- or Bed-to-Chair Transfer Admission Performance | 0–4 (average of 3 items) |
| GG0170F1—Mobility: Toilet Transfer Admission Performance | 0–4 (average of 3 items) |
| GG0170J1—Mobility: Walk 50 Feet with 2 Turns | 0–4 (average of 2 items) |
| GG0170K1—Mobility: Walk 150 Feet | 0–4 (average of 2 items) |
We use the same scoring algorithm for the Nursing Functional Score, as shown in Table 11.
| Section GG Item | Functional Score Range |
|---|---|
| GG0130A1—Self-care: Eating | 0–4 |
| GG0130C1—Self-care: Toileting Hygiene | 0–4 |
| GG0170B1—Mobility: Sit to Lying | 0–4 (average of 2 items) |
| GG0170C1—Mobility: Lying to Sitting on Side of Bed | 0–4 (average of 2 items) |
| GG0170D1—Mobility: Sit to Stand | 0–4 (average of 3 items) |
| GG0170E1—Mobility: Chair- or Bed-to-Chair Transfer | 0–4 (average of 3 items) |
| GG0170F1—Mobility: Toilet Transfer | 0–4 (average of 3 items) |
These 12 SLP-related comorbidities predict higher SLP costs:
- Amyotrophic lateral sclerosis (ALS)
- Aphasia
- Apraxia
- Cerebrovascular accident (CVA), transient ischemic attack (TIA), or stroke
- Dysphagia
- Hemiplegia or hemiparesis
- Laryngeal cancer
- Oral cancers
- Speech and language deficits
- Tracheostomy care (while a resident)
- Traumatic brain injury
- Ventilator or respirator (while a resident)
PDPM has more information about mapping between ICD-10-CM diagnoses and SLP comorbidities.
Under the PDPM, we assess a patient’s cognitive status using the Brief Interview for Mental Status (BIMS). In cases where you can’t complete the BIMS, complete a Staff Assessment for Mental Status. We use the Cognitive Performance Scale (CPS) to assign patients a score based on the staff assessment responses. We base the new PDPM cognitive score on the Cognitive Function Scale, which combines scores from the BIMS and CPS into 1 scale that compares cognitive function across all patients.
After completing the BIMS or CPS, use the cognitive measure classification methodology in Table 12 to determine the BIMS and CPS scores.
| PDPM Cognitive Level | BIMS Score | CPS Score |
|---|---|---|
| Cognitively Intact | 13–15 | 0 |
| Mildly Impaired | 8–12 | 1–2 |
| Moderately Impaired | 0–7 | 3–4 |
| Severely Impaired | N/A | 5–6 |
NTA Comorbidity Score
We found NTA costs increase with 50 conditions and extensive services. Providers report these conditions and extensive services on the MDS 3.0 with the ICD-10-CM codes identified in MDS Item I8000.
The PDPM NTA accounts for the relative costliness of some comorbidity scores and comes from a patient’s weighted comorbidities count, rather than a simple comorbidities count.
To get this weighted count, we assign points between 1 and 8 to each of the 50 PDPM comorbidities to classify the patient’s NTA based on its relative costliness.
To determine the patient’s NTA comorbidity score:
- Identify all the patient’s qualifying comorbidities
- Add each comorbidity’s points
This sum is the patient’s NTA comorbidity score, putting that patient into an NTA component classification group.
Streamlined Assessment Schedule
PDPM PPS assessments include:
- Initial 5-day PPS assessment
- Interim Payment Assessment (IPA), an optional assessment completed at any point during the patient’s stay when clinical change occurs
- Discharge assessment
For late assessments, providers:
- Bill the default Health Insurance Prospective Payment System (HIPPS) late assessments code for non-compliant days
- Use the 5-day assessment HIPPS code for the rest of the stay unless the provider completes an IPA
Late assessments affect VPD. For example, if a 5-day assessment is 2 days late, we adjust VPD for days 1 and 2 and calculate it using the default HIPPS code. The 5-day assessment HIPPS code controls payment starting on day 3 of the VPD schedule.
PDPM HIPPS Coding
Each PDPM HIPPS code follows this structure:
- Character 1: PT and OT Payment Group
- Character 2: SLP Payment Group
- Character 3: Nursing Payment Group
- Character 4: NTA Payment Group
- Character 5: Assessment Indicator
IPA Item Set
Providers may complete the IPA to report the patient’s PDPM classification change with no VPD schedule change. The IPA changes payment starting on the assessment review date, ending when the Part A stay stops, unless the provider completes another IPA.
State Assessments
States can choose PDPM item sets to calculate Medicaid payments. Each state determines if providers use PDPM comparisons and payment data for Medicaid. If so, states may require Omnibus Budget Reconciliation Act PDPM assessment data, like comprehensive and quarterly assessments. These item sets use Section GG, Items I0020B (primary medical condition) and J2100 (recent surgery requiring active SNF care).
MDS 3.0 Technical Information has more information.
MDS Items
Section I: SNF Primary Diagnosis: Code Item I0020 as any response 1–13; then enter the ICD-10-CM code in I0020B to report a patient’s primary diagnosis. This item asks, “What’s the main reason for admitting this person to the SNF?” We retired Item I0020A; use only I0020 and I0020B.
Section J: Patient Surgical History: Items J2100 – J5000 capture major surgical procedures during the hospital stay immediately before SNF admission. We use these items with the diagnosis captured in I0020B to classify patients into PT and OT case-mix categories.
Section O: Discharge Therapy Items: Items O0425A1 – O0425C5 record each therapy discipline mode (for example, individual, group, or concurrent therapy) and therapy amount (in minutes) the patient gets. Users get an error message if that discipline’s group and concurrent minutes total more than 25% of total therapy.
Section GG: Interim Performance: To get a patient’s interim performance, use MDS Section GG items, column 5, for patient functional assessments. This column’s look-back period is a 3-day window before the IPA’s assessment reference date.
Non-critical access hospital swing bed facilities must complete the Swing Bed PPS PDPM Assessment.
MDS 3.0 for Nursing Homes and Swing Bed Providers and MDS 3.0 Resident Assessment Instrument Manual have more information on swing beds.
Concurrent & Group Therapy Limit
The PDPM combined limit for both concurrent therapy (1 therapist with 2 patients doing different activities) and group therapy (1 therapist with 2–6 patients doing the same or similar activities) can’t equal more than 25% of the therapy that SNF patients get for each therapy discipline.
The PPS Discharge Assessment checks therapy limit compliance and includes the number of minutes per mode, per discipline, for the entire PPS stay.
Interrupted SNF Stay Policy
An interrupted SNF stay happens when a patient leaves Part A-covered SNF care and then readmitted to Part A-covered SNF care in the same SNF (not a different SNF) within the interruption window.
Note: If a resident drops to a non-skilled level of care or leaves Part A SNF care, we consider the patient discharged because of the interrupted stay policy, even if the patient remains in the facility.
The interruption window is a 3-day period starting on the first non-covered day after a Part A-covered SNF stay and ending at 11:59 pm on the third consecutive non-covered day.
The first non-covered day is:
- The departure day if the patient leaves the SNF
- The day after the final Part A coverage day if the patient stops Part A coverage but stays in the SNF
If the patient returns to a covered Part A stay within 3 days, we consider the subsequent stay a continuation of the last interrupted stay and:
- The VPD schedule continues from the last discharge day.
- The assessment schedule continues from the Part A discharge day. We don’t require a new 5-day assessment when the patient readmited, but the provider may decide to complete the IPA.
For example, if the SNF patient discharged from Part A on day 17 (in other words, day 17 is the last covered SNF day), payment rates start on day 18 upon readmission.
The interrupted stay policy doesn’t apply, and we consider the subsequent stay a new stay, if the patient readmited to either:
- The same SNF outside the interruption window
- A different SNF (regardless of the length of time between stays)
In these cases, the VPD schedule resets to day 1 payment rates, and the assessment schedule also resets to day 1, requiring a new 5-day assessment.
Administrative Level-of-Care Presumption Under PDPM
SNF PPS administrative presumption automatically classifies a patient who’s correctly assigned 1 of the designated, more intensive case-mix classifiers on the 5-day PPS assessment to a SNF level of care through the assessment reference date.
Patients not assigned to a designated classifier get an individual determination using existing administrative criteria. This doesn’t automatically classify the patient as meeting or not meeting the level-of-care definition.
PDPM classifiers designated under this administrative presumption include:
- Nursing groups covered by the Extensive Services, Special Care High, Special Care Low, and Clinically Complex nursing categories
- PT and OT groups TA, TB, TC, TD, TE, TF, TG, TJ, TK, TN, and TO
- SLP groups SC, SE, SF, SH, SI, SJ, SK, and SL
- NTA component’s uppermost (12+) comorbidity group
PDPM Payment for AIDS Patients
PDPM focuses AIDS patient costs by assigning the highest classification point value (8 points) of any condition or service under its NTA component and adds 18% to the nursing component.
The CB provision is like hospital bundling and requires SNFs to include all Medicare-covered services a patient gets during a covered Part A stay on the Part A bill, except a small list of excluded services billed separately under Part B by an outside entity.
For Part A-covered patient stays, the CB provision requires SNFs to bill us for all patient PT, OT, and SLP services. Submit all Part A-stay claim services performed by an outside entity, except specifically excluded services outside the PPS bundle, which are separately billable under Part B.
We exclude some services from CB. The CB exclusion doesn’t apply to a physician’s “incident to” services provided by someone else as incident to the practitioner’s professional service. When someone else provides an incident to service to a SNF resident, we treat it as a CB item, so the SNF must bill us for it. The Consolidated Appropriations Act, 2023 excludes coverage for marriage and family therapists and mental health counselors from CB.
Learn more about CB in the SNF Consolidated Billing web-based training course.
Place of service (POS) codes identify where a patient gets a service. Enter the correct 2-digit code on Medicare claims to ensure proper payment for physician services provided to patients in inpatient facilities like SNFs and hospitals. POS codes frequently associated with SNF services include:
- Inpatient hospital: 21
- SNF (with Part A coverage): 31
- Nursing facility or SNF (with no Part A coverage): 32
An Office of Inspector General report revealed that physicians sometimes enter POS code 32, indicating they provided patient services in a nursing facility or during a non-covered SNF stay when, in fact, the patient was covered under Part A. Use POS code 31 for services you provide during a Part A stay in a SNF.
Additionally, if a patient is seen in a physician’s office but is also a:
- Hospital inpatient, use POS code 21 for inpatient hospital
- SNF patient (with Part A coverage), use POS code 31 for SNF
- Nursing facility or SNF patient (without Part A coverage), use POS code 32 for nursing facility
MLN Matters® article MM13767 has more information.
The SNF Quality Reporting Program (QRP) provides quality-of-care information so patients can make informed decisions about their health care options. It also encourages facilities and providers to improve their quality of inpatient care by making sure they’re aware of, and reporting on, best practices.
The SNF QRP applies to freestanding SNFs, SNFs affiliated with acute care facilities, all non-critical access hospitals, and non-swing bed rural hospitals.
SNF QRP Measures and Technical Information has the current quality reporting measures. Find more information in the SNF QRP FAQs.
To meet the SNF QRP requirements, SNFs must submit Resident Assessment Instrument MDS quality data and the CDC National Healthcare Safety Network summary data. Any SNF we determine to be non-compliant with the quality reporting requirements may be subject to a 2 percentage-point reduction in its annual payment update for the applicable year.
Starting with residents admitted on October 1, 2029—for the purposes of the FY 2031 SNF QRP—we’ll require SNFs to submit MDS data for all SNF residents, regardless of payer. We’ll include new items in the MDS Type of Assessment section to indicate if the patient isn’t a Medicare Fee-for-Service (FFS) patient. We won’t include data on non-Medicare FFS residents in policy changes.
SNFs may qualify for a QRP reconsideration and an exception or extension.
Through the SNF VBP Program, we award incentive payments to encourage SNFs to improve the quality of care they provide to patients.
We reduce the adjusted federal per diem rate by 2% and adjust the resulting rate by the earned FY SNF amount.
For the FY 2027 Program year, the SNF VBP will use 8 quality measures.
For the FYs 2019–2025 Program years, we used only the SNF 30-Day All-Cause Readmission Measure (SNFRM) to evaluate SNFs in the SNF VBP Program. The Program ties portions of SNFs’ payments to their performance on this measure. We calculate this measure by assessing the risk-standardized rate of all-cause, unplanned hospital readmissions for Medicare FFS SNF patients within 30 days of discharge from a previous nearby hospitalization.
We’re replacing the SNFRM with the SNF Within-Stay Potentially Preventable Readmission (SNF WS PPR) starting with the FY 2028 Program year. FY 2027 will be the last Program year we include the SNFRM.
SNFs get quarterly and annual performance reports, which we use to publicly report SNF performance information on Care Compare.
42 CFR 413.338 has more information on the VBP Program.